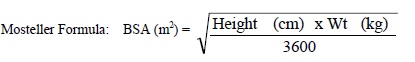nevirapine 200 MG Oral Tablet — Non-nucleoside reverse transcriptase inhibitors. INDICATIONS AND USAGE Nevirapine tablets, USP are indicated for use in combination with other antiretroviral agents for the treatment of HIV-1…
Boxed warning
WARNING: LIFE-THREATENING (INCLUDING FATAL) HEPATOTOXICITY and SKIN REACTIONS HEPATOTOXICITY: Severe, life-threatening, and in some cases fatal hepatotoxicity, particularly in the first 18 weeks, has been reported in patients treated with nevirapine. In some cases, patients presented with non-specific prodromal signs or symptoms of hepatitis and progressed to hepatic failure. These events are often associated with rash. Female sex and higher CD4 + cell counts at initiation of therapy place patients at increased risk; women with CD4 + cell counts greater than 250 cells/mm 3 , including pregnant women receiving nevirapine in combination with other antiretrovirals for the treatment of HIV-1 infection, are at the greatest risk. However, hepatotoxicity associated with nevirapine use can occur in both sexes, all CD4 + cell counts and at any time during treatment. Hepatic failure has also been reported in patients without HIV taking nevirapine for post-exposure prophylaxis (PEP). Use of nevirapine for occupational and non-occupational PEP is contraindicated [see Contraindications (4) ]. Patients with signs or symptoms of hepatitis, or with increased transaminases combined with rash or other systemic symptoms, must discontinue nevirapine and seek medical evaluation immediately [see Warnings and Precautions (5.1) ]. SKIN REACTIONS: Severe, life-threatening skin reactions, including fatal cases, have occurred in patients treated with nevirapine. These have included cases of Stevens-Johnson syndrome, toxic epidermal necrolysis, and hypersensitivity reactions characterized by rash, constitutional findings, and organ dysfunction. Patients developing signs or symptoms of severe skin reactions or hypersensitivity reactions must discontinue nevirapine and seek medical evaluation immediately. Transaminase levels should be checked immediately for all patients who develop a rash in the first 18 weeks of treatment. The 14-day lead-in period with immediate-release nevirapine 200 mg daily dosing has been observed to decrease the incidence of rash and must be followed [see Warnings and Precautions (5.2) ]. MONITORING FOR HEPATOTOXICITY AND SKIN REACTIONS: Patients must be monitored intensively during the first 18 weeks of therapy with nevirapine to detect potentially life-threatening hepatotoxicity or skin reactions. Extra vigilance is warranted during the first 6 weeks of therapy, which is the period of greatest risk of these events. Do not restart nevirapine following clinical hepatitis, or transaminase elevations combined with rash or other systemic symptoms, or following severe skin rash or hypersensitivity reactions. In some cases, hepatic injury has progressed despite discontinuation of treatment. WARNING: LIFE-THREATENING (INCLUDING FATAL) HEPATOTOXICITY and SKIN REACTIONS See full prescribing information for complete boxed warning. • Fatal and non-fatal hepatotoxicity have been reported in patients taking nevirapine extended-release tablets. Discontinue immediately if clinical hepatitis or transaminase elevations combined with rash or other systemic symptoms occur. Do not restart nevirapine extended-release tablets after recovery. (5.1) • Fatal and non-fatal skin reactions, including Stevens-Johnson syndrome, toxic epidermal necrolysis, and hypersensitivity reactions, have been reported. Discontinue immediately if severe skin reactions, hypersensitivity reactions, or any rash with systemic symptoms occur. Check transaminase levels immediately for all patients who develop a rash in the first 18 weeks of treatment. Do not restart nevirapine extended-release tablets after recovery. ( 5.2 ) • Monitoring during the first 18 weeks of therapy is essential. Extra vigilance is warranted during the first 6 weeks of therapy, which is the period of greatest risk of these events. ( 5.1 , 5.2 )
INDICATIONS AND USAGE Nevirapine tablets, USP are indicated for use in combination with other antiretroviral agents for the treatment of HIV-1 infection. This indication is based on one principal clinical trial (BI 1090) that demonstrated prolonged suppression of HIV-1 RNA and two smaller supportive trials, one of which (BI 1046) is described below. Additional important information regarding the use of Nevirapine tablets, USP for the treatment of HIV-1 infection: Based on serious and life-threatening hepatotoxicity observed in controlled and uncontrolled trials, Nevirapine tablets, USP should not be initiated in adult females with CD4 + cell counts greater than 250 cells/mm 3 or in adult males with CD4 + cell counts greater than 400 cells/mm 3 unless the benefit outweighs the risk [ see Boxed Warning and Warnings and Precautions (5.1) ]. The 14-day lead-in period with Nevirapine tablets, USP 200 mg daily dosing must be strictly followed; it has been demonstrated to reduce the frequency of rash [ see Dosage and Administration (2.4) and Warnings and Precautions (5.2) ]. If rash persists beyond the 14-day lead-in period, do not dose escalate to 200 mg twice daily. The 200 mg once-daily dosing regimen should not be continued beyond 28 days, at which point an alternative regimen should be sought. Nevirapine tablets, USP are an NNRTI indicated for combination antiretroviral treatment of HIV-1 infection (1) Important Considerations: Initiation of treatment is not recommended in the following populations unless the benefits outweigh the risks (1, 5.1) adult females with CD4 + cell counts greater than 250 cells/mm 3 adult males with CD4 + cell counts greater than 400 cells/mm 3 The 14-day lead-in period must be strictly followed; it has been demonstrated to reduce the frequency of rash (2.4, 5.2)
Dosage
DOSAGE & ADMINISTRATION • The 14-day lead-in period with immediate-release nevirapine tablets (200 mg once daily) must be strictly followed; it has been demonstrated to reduce the frequency of rash. ( 2.5 , 5.2 ) • Must be swallowed whole and must not be chewed, crushed, or divided. ( 2.1 ) • Adult patients must initiate therapy with one 200 mg immediate-release nevirapine tablet once daily for the first 14 days, followed by one 400 mg tablet of nevirapine extended-release tablets once daily. ( 2.2 ) • Adult patients already on a regimen of immediate-release nevirapine tablets twice daily can be switched to nevirapine extended-release tablets 400 mg once daily without the 14-day lead-in period of immediate-release nevirapine tablets. ( 2.2 ) • Pediatric patients (ages 6 to less than 18 years with a BSA of 1.17 m 2 or greater) must initiate therapy with immediate-release nevirapine tablets (as 150 mg/m2 of Nevirapine Oral Suspension or as nevirapine tablet) at a dose not to exceed 200 mg per day administered once daily for the first 14 days, followed by nevirapine extended-release tablets 400 mg once daily. ( 2.3 ) • Pediatric patients with a BSA of 1.17 m 2 or greater already on a regimen of twice daily nevirapine tablets Oral Suspension or immediate-release nevirapine can be switched to nevirapine extended-release tablets 400 mg once daily without the 14-day lead-in period of nevirapine Oral Suspension or immediate-release nevirapine tablets. ( 2.3 ) • If any patient experiences rash during the 14-day lead-in period with immediate-release nevirapine tablets do not initiate nevirapine extended-release tablets until the rash has resolved. Do not continue the immediate-release nevirapine tablets lead-in dosing regimen beyond 28 days. ( 2.5 ) • If dosing is interrupted for greater than 7 days, restart 14-day lead-in dosing. ( 2.5 ) 2.1 General Dosing Considerations Nevirapine extended-release tablets must be swallowed whole and must not be chewed, crushed, or divided. Pediatric patients should be assessed for their ability to swallow the extended-release tablets before prescribing nevirapine extended-release tablets. Nevirapine extended-release tablets can be taken with or without food. 2.2 Recommended Dosage in Adult Patients Patients not currently taking immediate-release nevirapine Patients must initiate therapy with one 200-mg tablet of immediate-release nevirapine tablets daily for the first 14 days in combination with other antiretroviral agents. The 14-day lead-in period with nevirapine tablets 200 mg daily dosing must be strictly followed (the lead-in period has been observed to decrease the incidence of rash), followed by one 400-mg tablet of nevirapine extended-release tablets once daily [see Dosage and Administration ( 2.5 ) and Warnings and Precautions ( 5.2 )]. If rash persists beyond the 14-day lead-in period with immediate-release nevirapine tablets, do not begin dosing with nevirapine extended-release tablets. The lead-in dosing with 200 mg once daily immediate-release nevirapine tablets should not be continued beyond 28 days, at which point an alternative regimen should be sought. Switching patients from immediate-release nevirapine tablets to nevirapine extended-release tablets Patients already on a regimen of immediate-release nevirapine tablets twice daily in combination with other antiretroviral agents can be switched to nevirapine extended-release tablets 400 mg once daily without the 14-day lead-in period. Patients already on a regimen of immediate-release nevirapine tablets twice daily who switch to nevirapine extended-release tablets therapy should continue with their ongoing clinical and laboratory monitoring. 2.3 Recommended Dosage in Pediatric Patients Nevirapine extended-release tablet in pediatric patients is dosed based on body surface area (BSA) calculated using the Mosteller formula. All pediatric patients must initiate therapy with immediate-release nevirapine tablets (as 150 mg/m 2 of Nevirapine Oral Suspension or as nevirapine tablets), at a dose not to exceed 200 mg per day, administered once daily for the first 14 days. This lead-in period should be used because it has been demonstrated to reduce the frequency of rash. This lead-in period is not required if the patient is already on a regimen of twice daily immediate-release formulation in combination with other antiretroviral agents. The recommended oral dosage of nevirapine extended-release tablets for pediatric patients with a BSA of 1.17 m 2 or greater is 400 mg following the lead-in period with immediate-release nevirapine tablets. The total daily dose should not exceed 400 mg for any patient. formula 2.4 Monitoring of Patients Intensive clinical and laboratory monitoring, including liver enzyme tests, is essential at baseline and during the first 18 weeks of treatment with nevirapine. The optimal frequency of monitoring during this period has not been established. Some experts recommend clinical and laboratory monitoring more often than once per month, and in particular, would include monitoring of liver enzyme tests prior to beginning the 14-day lead-in period with immediate-release nevirapine tablets, prior to initiation of nevirapine extended-release tablets, and at two weeks after initiation of nevirapine extended-release tablets therapy. After the initial 18-week period, frequent clinical and laboratory monitoring should continue throughout nevirapine extended-release tablets treatment [see Warnings and Precautions ( 5 )]. In some cases, hepatic injury has progressed despite discontinuation of treatment. Patients already on a regimen of immediate-release nevirapine tablets twice daily who switch to nevirapine extended-release tablets once daily should continue with their ongoing clinical and laboratory monitoring. 2.5 Dosage Adjustment Patients with Rash Discontinue nevirapine if a patient experiences severe rash or any rash accompanied by constitutional findings [see Boxed Warning, Warnings and Precautions ( 5.2 )]. Do not initiate therapy with nevirapine extended-release tablets if a patient experiences mild to moderate rash without constitutional symptoms during the 14-day lead-in period of immediate-release nevirapine tablets until the rash has resolved [see Warnings and Precautions ( 5.2 )]. The total duration of the once daily lead-in dosing period should not exceed 28 days, at which point an alternative regimen should be sought. Patients with Hepatic Events If a clinical (symptomatic) hepatic event occurs, permanently discontinue nevirapine. Do not restart nevirapine after recovery [see Warnings and Precautions ( 5.1 )]. Patients with Dose Interruption For patients who interrupt nevirapine extended-release tablets dosing for more than 7 days, restart the recommended lead-in dosing with immediate-release nevirapine tablets, using one 200 mg tablet daily for the first 14 days. Patients with Renal Impairment Patients with CrCl greater than or equal to 20 mL per min and not requiring dialysis do not require an adjustment in dosing. The pharmacokinetics of nevirapine have not been evaluated in patients with CrCl less than 20 mL per min. An additional 200 mg dose of immediate-release nevirapine tablets following each dialysis treatment is indicated in patients requiring dialysis. Nevirapine metabolites may accumulate in patients receiving dialysis; however, the clinical significance of this accumulation is not known [see Clinical Pharmacology ( 12.3 )]. Nevirapine extended-release tablets have not been studied in patients with renal dysfunction.
Warnings
WARNINGS AND PRECAUTIONS • Monitor patients for immune reconstitution syndrome and fat redistribution. ( 5.5 , 5.6 ) 5.1 Hepatotoxicity and Hepatic Impairment Severe, life-threatening, and in some cases fatal hepatotoxicity, including fulminant and cholestatic hepatitis, hepatic necrosis and hepatic failure, have been reported in patients treated with nevirapine. The risk of symptomatic hepatic events regardless of severity is greatest in the first 6 weeks of therapy. The risk continued to be greater in the nevirapine groups in controlled clinical trials through 18 weeks of treatment. However, hepatic events may occur at any time during treatment. In some cases, patients presented with non-specific, prodromal signs or symptoms of fatigue, malaise, anorexia, nausea, jaundice, liver tenderness or hepatomegaly, with or without initially abnormal serum transaminase levels. Rash was observed in approximately half of the patients with symptomatic hepatic adverse events. Fever and flu-like symptoms accompanied some of these hepatic events. Some events, particularly those with rash and other symptoms, have progressed to hepatic failure with transaminase elevation, with or without hyperbilirubinemia, hepatic encephalopathy, prolonged partial thromboplastin time, or eosinophilia. Rhabdomyolysis has been observed in some patients experiencing skin and/or liver reactions associated with nevirapine use. Hepatitis/hepatic failure may be associated with signs of hypersensitivity which can include severe rash or rash accompanied by fever, general malaise, fatigue, muscle or joint aches, blisters, oral lesions, conjunctivitis, facial edema, eosinophilia, granulocytopenia, lymphadenopathy, or renal dysfunction. Patients with signs or symptoms of hepatitis must be advised to discontinue nevirapine and immediately seek medical evaluation, which should include liver enzyme tests. The first 18 weeks of therapy with nevirapine extended-release tablets are a critical period during which intensive clinical and laboratory monitoring of patients is required to detect potentially life-threatening hepatic events. The optimal frequency of monitoring during this period has not been established. Some experts recommend clinical and laboratory monitoring more often than once per month, and in particular, include monitoring of liver enzyme tests at baseline, prior to dose escalation and at two weeks post-dose escalation. After the initial 18-week period, frequent clinical and laboratory monitoring should continue throughout nevirapine extended-release tablets treatment. Transaminases should be checked immediately if a patient experiences signs or symptoms suggestive of hepatitis and/or hypersensitivity reaction. Transaminases should also be checked immediately for all patients who develop a rash in the first 18 weeks of treatment. Physicians and patients should be vigilant for the appearance of signs or symptoms of hepatitis, such as fatigue, malaise, anorexia, nausea, jaundice, bilirubinuria, acholic stools, liver tenderness, or hepatomegaly. The diagnosis of hepatotoxicity should be considered in this setting, even if transaminases are initially normal or alternative diagnoses are possible [see Dosage and Administration ( 2.4 )]. If clinical hepatitis or transaminase elevations combined with rash or other systemic symptoms occur, permanently discontinue nevirapine. Do not restart nevirapine after recovery. In some cases, hepatic injury progresses despite discontinuation of treatment. The patients at greatest risk of hepatic events, including potentially fatal events, are women with high CD4 + cell counts. In a retrospective analysis of pooled clinical trials with immediate-release nevirapine tablets, during the first 6 weeks of treatment women had a 3-fold higher risk than men for symptomatic, often rash-associated, hepatic events (6% versus 2%). Patients with higher CD4 + cell counts at initiation of nevirapine therapy are at higher risk for symptomatic hepatic events. Women with CD4 + cell counts greater than 250 cells/mm 3 had a 12-fold higher risk of symptomatic hepatic adverse events compared to women with CD4 + cell counts less than 250 cells/mm 3 (11% versus 1%). An increased risk was observed in men with CD4 + cell counts greater than 400 cells/mm 3 (6% versus 1% for men with CD4 + cell counts less than 400 cells/mm 3 ). However, all patients, regardless of sex, CD4 + cell count, or antiretroviral treatment history, should be monitored for hepatotoxicity since symptomatic hepatic adverse events have been reported at all CD4 + cell counts. Co-infection with hepatitis B or C or transaminase elevations at the start of therapy with nevirapine are associated with a greater risk of later symptomatic events (6 weeks or more after starting nevirapine) and asymptomatic increases in AST or ALT. In addition, serious hepatotoxicity (including liver failure requiring transplantation in one instance) has been reported in HIV-1 uninfected individuals receiving multiple doses of immediate-release nevirapine tablets in the setting of post-exposure prophylaxis (PEP), an unapproved use. Use of nevirapine extended-release tablets for occupational and non-occupational PEP is contraindicated [see Contraindications ( 4 )]. Increased nevirapine trough concentrations have been observed in some patients with hepatic fibrosis or cirrhosis. Therefore, carefully monitor patients with either hepatic fibrosis or cirrhosis for evidence of drug-induced toxicity. Do not administer nevirapine to patients with moderate or severe (Child-Pugh Class B or C, respectively) hepatic impairment [see Contraindications ( 4 ), Use in Specific Populations ( 8.7 ), and Clinical Pharmacology ( 12.3 )]. Nevirapine extended-release tablets have not been evaluated in subjects with hepatic impairment. 5.2 Skin Reactions Severe and life-threatening skin reactions, including fatal cases, have been reported in patients taking nevirapine. These have occurred most frequently during the first 6 weeks of therapy. These have included cases of Stevens-Johnson syndrome, toxic epidermal necrolysis, and hypersensitivity reactions characterized by rash, constitutional findings, and organ dysfunction including hepatic failure. Rhabdomyolysis has been observed in some patients experiencing skin and/or liver reactions associated with nevirapine use. Patients developing signs or symptoms of severe skin reactions or hypersensitivity reactions (including, but not limited to, severe rash or rash accompanied by fever, general malaise, fatigue, muscle or joint aches, blisters, oral lesions, conjunctivitis, facial edema, and/or hepatitis, eosinophilia, granulocytopenia, lymphadenopathy, and renal dysfunction) must permanently discontinue nevirapine and seek medical evaluation immediately. Do not restart nevirapine following severe skin rash, skin rash combined with increased transaminases or other symptoms, or hypersensitivity reaction. The first 18 weeks of therapy with nevirapine extended-release tablets are a critical period during which intensive clinical and laboratory monitoring of patients is required to detect potentially life-threatening skin reactions. The optimal frequency of monitoring during this period has not been established. Some experts recommend clinical and laboratory monitoring more often than once per month, and in particular, include monitoring of liver enzyme tests at baseline, prior to dose escalation and at two weeks post-dose escalation. After the initial 18-week period, frequent clinical and laboratory monitoring should continue throughout nevirapine extended-release tablets treatment. In addition, the 14-day lead-in period with immediate-release nevirapine tablets 200 mg daily dosing has been demonstrated to reduce the frequency of rash [see Dosage and Administration ( 2.2 )]. If patients present with a suspected nevirapine-associated rash, measure transaminases immediately. Permanently discontinue nevirapine in patient
Contraindications
CONTRAINDICATIONS Patients with moderate or severe (Child-Pugh Class B or C, respectively) hepatic impairment (4.1, 5.1, 8.7) Use as part of occupational and non-occupational post-exposure prophylaxis (PEP) regimens, an unapproved use (4.2, 5.1) 4.1 Hepatic Impairment Nevirapine, USP is contraindicated in patients with moderate or severe (Child-Pugh Class B or C, respectively) hepatic impairment [ see Warnings and Precautions (5.1) and Use in Specific Populations (8.7) ]. 4.2 Post-Exposure Prophylaxis Nevirapine, USP is contraindicated for use as part of occupational and non-occupational post-exposure prophylaxis (PEP) regimens [ see Warnings and Precautions (5.1) ].
Mechanism of action
Mechanism of Action Nevirapine is an antiretroviral drug [see Microbiology (12.4) ]. Mechanism of Action Nevirapine is a non-nucleoside reverse transcriptase inhibitor (NNRTI) of HIV-1. Nevirapine binds directly to reverse transcriptase (RT) and blocks the RNA-dependent and DNA-dependent DNA polymerase activities by causing a disruption of the enzyme’s catalytic site. The activity of nevirapine does not compete with template or nucleoside triphosphates. HIV-2 RT and eukaryotic DNA polymerases (such as human DNA polymerases α, ß, γ, or δ) are not inhibited by nevirapine.
A drug lookup is just the start. Eleplan keeps the whole care plan in one place.
Medications, diagnoses, documents, appointments, and the whole care team — organized and always in sync, with Ellie, your AI care assistant, on top of it. Free to start.