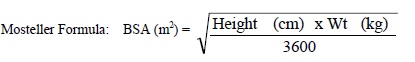Human Immunodeficiency Virus 1 Non-Nucleoside Analog Reverse Transcriptase Inhibitor [EPC] — ORAL
Nevirapine — Human Immunodeficiency Virus 1 Non-Nucleoside Analog Reverse Transcriptase Inhibitor [EPC]. INDICATIONS AND USAGE Nevirapine tablets, USP are indicated for use in combination with other antiretroviral agents for the treatment of HIV-1…
Boxed warning
WARNING: LIFE-THREATENING (INCLUDING FATAL) HEPATOTOXICITY and SKIN REACTIONS HEPATOTOXICITY: Severe, life-threatening, and in some cases fatal hepatotoxicity, particularly in the first 18 weeks, has been reported in patients treated with nevirapine. In some cases, patients presented with non-specific prodromal signs or symptoms of hepatitis and progressed to hepatic failure. These events are often associated with rash. Female sex and higher CD4 + cell counts at initiation of therapy place patients at increased risk; women with CD4 + cell counts greater than 250 cells/mm 3 , including pregnant women receiving nevirapine in combination with other antiretrovirals for the treatment of HIV-1 infection, are at the greatest risk. However, hepatotoxicity associated with nevirapine use can occur in both sexes, all CD4 + cell counts and at any time during treatment. Hepatic failure has also been reported in patients without HIV taking nevirapine for post-exposure prophylaxis (PEP). Use of nevirapine for occupational and non-occupational PEP is contraindicated [see Contraindications (4) ]. Patients with signs or symptoms of hepatitis, or with increased transaminases combined with rash or other systemic symptoms, must discontinue nevirapine and seek medical evaluation immediately [see Warnings and Precautions (5.1) ]. SKIN REACTIONS: Severe, life-threatening skin reactions, including fatal cases, have occurred in patients treated with nevirapine. These have included cases of Stevens-Johnson syndrome, toxic epidermal necrolysis, and hypersensitivity reactions characterized by rash, constitutional findings, and organ dysfunction. Patients developing signs or symptoms of severe skin reactions or hypersensitivity reactions must discontinue nevirapine and seek medical evaluation immediately. Transaminase levels should be checked immediately for all patients who develop a rash in the first 18 weeks of treatment. The 14-day lead-in period with immediate-release nevirapine 200 mg daily dosing has been observed to decrease the incidence of rash and must be followed [see Warnings and Precautions (5.2) ]. MONITORING FOR HEPATOTOXICITY AND SKIN REACTIONS: Patients must be monitored intensively during the first 18 weeks of therapy with nevirapine to detect potentially life-threatening hepatotoxicity or skin reactions. Extra vigilance is warranted during the first 6 weeks of therapy, which is the period of greatest risk of these events. Do not restart nevirapine following clinical hepatitis, or transaminase elevations combined with rash or other systemic symptoms, or following severe skin rash or hypersensitivity reactions. In some cases, hepatic injury has progressed despite discontinuation of treatment. WARNING: LIFE-THREATENING (INCLUDING FATAL) HEPATOTOXICITY and SKIN REACTIONS See full prescribing information for complete boxed warning. • Fatal and non-fatal hepatotoxicity have been reported in patients taking nevirapine extended-release tablets. Discontinue immediately if clinical hepatitis or transaminase elevations combined with rash or other systemic symptoms occur. Do not restart nevirapine extended-release tablets after recovery. (5.1) • Fatal and non-fatal skin reactions, including Stevens-Johnson syndrome, toxic epidermal necrolysis, and hypersensitivity reactions, have been reported. Discontinue immediately if severe skin reactions, hypersensitivity reactions, or any rash with systemic symptoms occur. Check transaminase levels immediately for all patients who develop a rash in the first 18 weeks of treatment. Do not restart nevirapine extended-release tablets after recovery. ( 5.2 ) • Monitoring during the first 18 weeks of therapy is essential. Extra vigilance is warranted during the first 6 weeks of therapy, which is the period of greatest risk of these events. ( 5.1 , 5.2 )
INDICATIONS AND USAGE Nevirapine tablets, USP are indicated for use in combination with other antiretroviral agents for the treatment of HIV-1 infection. This indication is based on one principal clinical trial (BI 1090) that demonstrated prolonged suppression of HIV-1 RNA and two smaller supportive trials, one of which (BI 1046) is described below. Additional important information regarding the use of Nevirapine tablets, USP for the treatment of HIV-1 infection: Based on serious and life-threatening hepatotoxicity observed in controlled and uncontrolled trials, Nevirapine tablets, USP should not be initiated in adult females with CD4 + cell counts greater than 250 cells/mm 3 or in adult males with CD4 + cell counts greater than 400 cells/mm 3 unless the benefit outweighs the risk [ see Boxed Warning and Warnings and Precautions (5.1) ]. The 14-day lead-in period with Nevirapine tablets, USP 200 mg daily dosing must be strictly followed; it has been demonstrated to reduce the frequency of rash [ see Dosage and Administration (2.4) and Warnings and Precautions (5.2) ]. If rash persists beyond the 14-day lead-in period, do not dose escalate to 200 mg twice daily. The 200 mg once-daily dosing regimen should not be continued beyond 28 days, at which point an alternative regimen should be sought. Nevirapine tablets, USP are an NNRTI indicated for combination antiretroviral treatment of HIV-1 infection (1) Important Considerations: Initiation of treatment is not recommended in the following populations unless the benefits outweigh the risks (1, 5.1) adult females with CD4 + cell counts greater than 250 cells/mm 3 adult males with CD4 + cell counts greater than 400 cells/mm 3 The 14-day lead-in period must be strictly followed; it has been demonstrated to reduce the frequency of rash (2.4, 5.2)
Dosage
DOSAGE & ADMINISTRATION • The 14-day lead-in period with immediate-release nevirapine tablets (200 mg once daily) must be strictly followed; it has been demonstrated to reduce the frequency of rash. ( 2.5 , 5.2 ) • Must be swallowed whole and must not be chewed, crushed, or divided. ( 2.1 ) • Adult patients must initiate therapy with one 200 mg immediate-release nevirapine tablet once daily for the first 14 days, followed by one 400 mg tablet of nevirapine extended-release tablets once daily. ( 2.2 ) • Adult patients already on a regimen of immediate-release nevirapine tablets twice daily can be switched to nevirapine extended-release tablets 400 mg once daily without the 14-day lead-in period of immediate-release nevirapine tablets. ( 2.2 ) • Pediatric patients (ages 6 to less than 18 years with a BSA of 1.17 m 2 or greater) must initiate therapy with immediate-release nevirapine tablets (as 150 mg/m2 of Nevirapine Oral Suspension or as nevirapine tablet) at a dose not to exceed 200 mg per day administered once daily for the first 14 days, followed by nevirapine extended-release tablets 400 mg once daily. ( 2.3 ) • Pediatric patients with a BSA of 1.17 m 2 or greater already on a regimen of twice daily nevirapine tablets Oral Suspension or immediate-release nevirapine can be switched to nevirapine extended-release tablets 400 mg once daily without the 14-day lead-in period of nevirapine Oral Suspension or immediate-release nevirapine tablets. ( 2.3 ) • If any patient experiences rash during the 14-day lead-in period with immediate-release nevirapine tablets do not initiate nevirapine extended-release tablets until the rash has resolved. Do not continue the immediate-release nevirapine tablets lead-in dosing regimen beyond 28 days. ( 2.5 ) • If dosing is interrupted for greater than 7 days, restart 14-day lead-in dosing. ( 2.5 ) 2.1 General Dosing Considerations Nevirapine extended-release tablets must be swallowed whole and must not be chewed, crushed, or divided. Pediatric patients should be assessed for their ability to swallow the extended-release tablets before prescribing nevirapine extended-release tablets. Nevirapine extended-release tablets can be taken with or without food. 2.2 Recommended Dosage in Adult Patients Patients not currently taking immediate-release nevirapine Patients must initiate therapy with one 200-mg tablet of immediate-release nevirapine tablets daily for the first 14 days in combination with other antiretroviral agents. The 14-day lead-in period with nevirapine tablets 200 mg daily dosing must be strictly followed (the lead-in period has been observed to decrease the incidence of rash), followed by one 400-mg tablet of nevirapine extended-release tablets once daily [see Dosage and Administration ( 2.5 ) and Warnings and Precautions ( 5.2 )]. If rash persists beyond the 14-day lead-in period with immediate-release nevirapine tablets, do not begin dosing with nevirapine extended-release tablets. The lead-in dosing with 200 mg once daily immediate-release nevirapine tablets should not be continued beyond 28 days, at which point an alternative regimen should be sought. Switching patients from immediate-release nevirapine tablets to nevirapine extended-release tablets Patients already on a regimen of immediate-release nevirapine tablets twice daily in combination with other antiretroviral agents can be switched to nevirapine extended-release tablets 400 mg once daily without the 14-day lead-in period. Patients already on a regimen of immediate-release nevirapine tablets twice daily who switch to nevirapine extended-release tablets therapy should continue with their ongoing clinical and laboratory monitoring. 2.3 Recommended Dosage in Pediatric Patients Nevirapine extended-release tablet in pediatric patients is dosed based on body surface area (BSA) calculated using the Mosteller formula. All pediatric patients must initiate therapy with immediate-release nevirapine tablets (as 150 mg/m 2 of Nevirapine Oral Suspension or as nevirapine tablets), at a dose not to exceed 200 mg per day, administered once daily for the first 14 days. This lead-in period should be used because it has been demonstrated to reduce the frequency of rash. This lead-in period is not required if the patient is already on a regimen of twice daily immediate-release formulation in combination with other antiretroviral agents. The recommended oral dosage of nevirapine extended-release tablets for pediatric patients with a BSA of 1.17 m 2 or greater is 400 mg following the lead-in period with immediate-release nevirapine tablets. The total daily dose should not exceed 400 mg for any patient. formula 2.4 Monitoring of Patients Intensive clinical and laboratory monitoring, including liver enzyme tests, is essential at baseline and during the first 18 weeks of treatment with nevirapine. The optimal frequency of monitoring during this period has not been established. Some experts recommend clinical and laboratory monitoring more often than once per month, and in particular, would include monitoring of liver enzyme tests prior to beginning the 14-day lead-in period with immediate-release nevirapine tablets, prior to initiation of nevirapine extended-release tablets, and at two weeks after initiation of nevirapine extended-release tablets therapy. After the initial 18-week period, frequent clinical and laboratory monitoring should continue throughout nevirapine extended-release tablets treatment [see Warnings and Precautions ( 5 )]. In some cases, hepatic injury has progressed despite discontinuation of treatment. Patients already on a regimen of immediate-release nevirapine tablets twice daily who switch to nevirapine extended-release tablets once daily should continue with their ongoing clinical and laboratory monitoring. 2.5 Dosage Adjustment Patients with Rash Discontinue nevirapine if a patient experiences severe rash or any rash accompanied by constitutional findings [see Boxed Warning, Warnings and Precautions ( 5.2 )]. Do not initiate therapy with nevirapine extended-release tablets if a patient experiences mild to moderate rash without constitutional symptoms during the 14-day lead-in period of immediate-release nevirapine tablets until the rash has resolved [see Warnings and Precautions ( 5.2 )]. The total duration of the once daily lead-in dosing period should not exceed 28 days, at which point an alternative regimen should be sought. Patients with Hepatic Events If a clinical (symptomatic) hepatic event occurs, permanently discontinue nevirapine. Do not restart nevirapine after recovery [see Warnings and Precautions ( 5.1 )]. Patients with Dose Interruption For patients who interrupt nevirapine extended-release tablets dosing for more than 7 days, restart the recommended lead-in dosing with immediate-release nevirapine tablets, using one 200 mg tablet daily for the first 14 days. Patients with Renal Impairment Patients with CrCl greater than or equal to 20 mL per min and not requiring dialysis do not require an adjustment in dosing. The pharmacokinetics of nevirapine have not been evaluated in patients with CrCl less than 20 mL per min. An additional 200 mg dose of immediate-release nevirapine tablets following each dialysis treatment is indicated in patients requiring dialysis. Nevirapine metabolites may accumulate in patients receiving dialysis; however, the clinical significance of this accumulation is not known [see Clinical Pharmacology ( 12.3 )]. Nevirapine extended-release tablets have not been studied in patients with renal dysfunction.
Warnings
WARNINGS AND PRECAUTIONS • Monitor patients for immune reconstitution syndrome and fat redistribution. ( 5.5 , 5.6 ) 5.1 Hepatotoxicity and Hepatic Impairment Severe, life-threatening, and in some cases fatal hepatotoxicity, including fulminant and cholestatic hepatitis, hepatic necrosis and hepatic failure, have been reported in patients treated with nevirapine. The risk of symptomatic hepatic events regardless of severity is greatest in the first 6 weeks of therapy. The risk continued to be greater in the nevirapine groups in controlled clinical trials through 18 weeks of treatment. However, hepatic events may occur at any time during treatment. In some cases, patients presented with non-specific, prodromal signs or symptoms of fatigue, malaise, anorexia, nausea, jaundice, liver tenderness or hepatomegaly, with or without initially abnormal serum transaminase levels. Rash was observed in approximately half of the patients with symptomatic hepatic adverse events. Fever and flu-like symptoms accompanied some of these hepatic events. Some events, particularly those with rash and other symptoms, have progressed to hepatic failure with transaminase elevation, with or without hyperbilirubinemia, hepatic encephalopathy, prolonged partial thromboplastin time, or eosinophilia. Rhabdomyolysis has been observed in some patients experiencing skin and/or liver reactions associated with nevirapine use. Hepatitis/hepatic failure may be associated with signs of hypersensitivity which can include severe rash or rash accompanied by fever, general malaise, fatigue, muscle or joint aches, blisters, oral lesions, conjunctivitis, facial edema, eosinophilia, granulocytopenia, lymphadenopathy, or renal dysfunction. Patients with signs or symptoms of hepatitis must be advised to discontinue nevirapine and immediately seek medical evaluation, which should include liver enzyme tests. The first 18 weeks of therapy with nevirapine extended-release tablets are a critical period during which intensive clinical and laboratory monitoring of patients is required to detect potentially life-threatening hepatic events. The optimal frequency of monitoring during this period has not been established. Some experts recommend clinical and laboratory monitoring more often than once per month, and in particular, include monitoring of liver enzyme tests at baseline, prior to dose escalation and at two weeks post-dose escalation. After the initial 18-week period, frequent clinical and laboratory monitoring should continue throughout nevirapine extended-release tablets treatment. Transaminases should be checked immediately if a patient experiences signs or symptoms suggestive of hepatitis and/or hypersensitivity reaction. Transaminases should also be checked immediately for all patients who develop a rash in the first 18 weeks of treatment. Physicians and patients should be vigilant for the appearance of signs or symptoms of hepatitis, such as fatigue, malaise, anorexia, nausea, jaundice, bilirubinuria, acholic stools, liver tenderness, or hepatomegaly. The diagnosis of hepatotoxicity should be considered in this setting, even if transaminases are initially normal or alternative diagnoses are possible [see Dosage and Administration ( 2.4 )]. If clinical hepatitis or transaminase elevations combined with rash or other systemic symptoms occur, permanently discontinue nevirapine. Do not restart nevirapine after recovery. In some cases, hepatic injury progresses despite discontinuation of treatment. The patients at greatest risk of hepatic events, including potentially fatal events, are women with high CD4 + cell counts. In a retrospective analysis of pooled clinical trials with immediate-release nevirapine tablets, during the first 6 weeks of treatment women had a 3-fold higher risk than men for symptomatic, often rash-associated, hepatic events (6% versus 2%). Patients with higher CD4 + cell counts at initiation of nevirapine therapy are at higher risk for symptomatic hepatic events. Women with CD4 + cell counts greater than 250 cells/mm 3 had a 12-fold higher risk of symptomatic hepatic adverse events compared to women with CD4 + cell counts less than 250 cells/mm 3 (11% versus 1%). An increased risk was observed in men with CD4 + cell counts greater than 400 cells/mm 3 (6% versus 1% for men with CD4 + cell counts less than 400 cells/mm 3 ). However, all patients, regardless of sex, CD4 + cell count, or antiretroviral treatment history, should be monitored for hepatotoxicity since symptomatic hepatic adverse events have been reported at all CD4 + cell counts. Co-infection with hepatitis B or C or transaminase elevations at the start of therapy with nevirapine are associated with a greater risk of later symptomatic events (6 weeks or more after starting nevirapine) and asymptomatic increases in AST or ALT. In addition, serious hepatotoxicity (including liver failure requiring transplantation in one instance) has been reported in HIV-1 uninfected individuals receiving multiple doses of immediate-release nevirapine tablets in the setting of post-exposure prophylaxis (PEP), an unapproved use. Use of nevirapine extended-release tablets for occupational and non-occupational PEP is contraindicated [see Contraindications ( 4 )]. Increased nevirapine trough concentrations have been observed in some patients with hepatic fibrosis or cirrhosis. Therefore, carefully monitor patients with either hepatic fibrosis or cirrhosis for evidence of drug-induced toxicity. Do not administer nevirapine to patients with moderate or severe (Child-Pugh Class B or C, respectively) hepatic impairment [see Contraindications ( 4 ), Use in Specific Populations ( 8.7 ), and Clinical Pharmacology ( 12.3 )]. Nevirapine extended-release tablets have not been evaluated in subjects with hepatic impairment. 5.2 Skin Reactions Severe and life-threatening skin reactions, including fatal cases, have been reported in patients taking nevirapine. These have occurred most frequently during the first 6 weeks of therapy. These have included cases of Stevens-Johnson syndrome, toxic epidermal necrolysis, and hypersensitivity reactions characterized by rash, constitutional findings, and organ dysfunction including hepatic failure. Rhabdomyolysis has been observed in some patients experiencing skin and/or liver reactions associated with nevirapine use. Patients developing signs or symptoms of severe skin reactions or hypersensitivity reactions (including, but not limited to, severe rash or rash accompanied by fever, general malaise, fatigue, muscle or joint aches, blisters, oral lesions, conjunctivitis, facial edema, and/or hepatitis, eosinophilia, granulocytopenia, lymphadenopathy, and renal dysfunction) must permanently discontinue nevirapine and seek medical evaluation immediately. Do not restart nevirapine following severe skin rash, skin rash combined with increased transaminases or other symptoms, or hypersensitivity reaction. The first 18 weeks of therapy with nevirapine extended-release tablets are a critical period during which intensive clinical and laboratory monitoring of patients is required to detect potentially life-threatening skin reactions. The optimal frequency of monitoring during this period has not been established. Some experts recommend clinical and laboratory monitoring more often than once per month, and in particular, include monitoring of liver enzyme tests at baseline, prior to dose escalation and at two weeks post-dose escalation. After the initial 18-week period, frequent clinical and laboratory monitoring should continue throughout nevirapine extended-release tablets treatment. In addition, the 14-day lead-in period with immediate-release nevirapine tablets 200 mg daily dosing has been demonstrated to reduce the frequency of rash [see Dosage and Administration ( 2.2 )]. If patients present with a suspected nevirapine-associated rash, measure transaminases immediately. Permanently discontinue nevirapine in patient
Contraindications
CONTRAINDICATIONS Patients with moderate or severe (Child-Pugh Class B or C, respectively) hepatic impairment (4.1, 5.1, 8.7) Use as part of occupational and non-occupational post-exposure prophylaxis (PEP) regimens, an unapproved use (4.2, 5.1) 4.1 Hepatic Impairment Nevirapine, USP is contraindicated in patients with moderate or severe (Child-Pugh Class B or C, respectively) hepatic impairment [ see Warnings and Precautions (5.1) and Use in Specific Populations (8.7) ]. 4.2 Post-Exposure Prophylaxis Nevirapine, USP is contraindicated for use as part of occupational and non-occupational post-exposure prophylaxis (PEP) regimens [ see Warnings and Precautions (5.1) ].
Drug interactions
DRUG INTERACTIONS Nevirapine is principally metabolized by the liver via the cytochrome P450 isoenzymes, 3A and 2B6. Nevirapine is known to be an inducer of these enzymes. As a result, drugs that are metabolized by these enzyme systems may have lower than expected plasma levels when co-administered with nevirapine. The results of drug interactions studies with immediate-release nevirapine tablets are expected to also apply to nevirapine extended-release tablets. The specific pharmacokinetic changes that occur with co-administration of nevirapine and other drugs are listed in Clinical Pharmacology , Table 4. Clinical comments about possible dosage modifications based on established drug interactions are listed in Table 3. The data in Tables 3 and 4 are based on the results of drug interaction studies conducted in HIV-1 seropositive subjects unless otherwise indicated. In addition to established drug interactions, there may be potential pharmacokinetic interactions between nevirapine and other drug classes that are metabolized by the cytochrome P450 system. These potential drug interactions are also listed in Table 3. Although specific drug interaction studies in HIV-1 seropositive subjects have not been conducted for some classes of drugs listed in Table 3, additional clinical monitoring may be warranted when co-administering these drugs. The in vitro interaction between nevirapine and the antithrombotic agent warfarin is complex. As a result, when giving these drugs concomitantly, plasma warfarin levels may change with the potential for increases in coagulation time. When warfarin is co-administered with nevirapine, anticoagulation levels should be monitored frequently. Table 3 Established and Potential Drug Interactions: Use with Caution, Alteration in Dose or Regimen May Be Needed Due to Drug Interaction Established Drug Interactions: See Clinical Pharmacology (12.3), Table 4 for Magnitude of Interaction. Drug Name Effect on Concentration of Nevirapine or Concomitant Drug Clinical Comment HIV Antiviral Agents: Protease Inhibitors (PIs) Atazanavir/Ritonavir* ↓ Atazanavir ↑ Nevirapine Do not co-administer nevirapine with atazanavir because nevirapine substantially decreases atazanavir exposure and there is a potential risk for nevirapine-associated toxicity due to increased nevirapine exposures. Fosamprenavir* ↓Amprenavir ↑Nevirapine Co-administration of nevirapine and fosamprenavir without ritonavir is not recommended. Fosamprenavir/Ritonavir* ↓Amprenavir ↑Nevirapine No dosing adjustments are required when nevirapine is co-administered with 700/100 mg of fosamprenavir/ritonavir twice daily. The combination of nevirapine administered with fosamprenavir/ritonavir once daily has not been studied. Indinavir* ↓ Indinavir The appropriate doses of this combination of indinavir and nevirapine with respect to efficacy and safety have not been established. Lopinavir/Ritonavir* ↓Lopinavir Dosing in adult patients: A dose adjustment of lopinavir/ritonavir to 500/125 mg tablets twice daily or 533/133 mg (6.5 mL) oral solution twice daily is recommended when used in combination with nevirapine. Neither lopinavir/ritonavir tablets nor oral solution should be administered once daily in combination with nevirapine. Dosing in pediatric patients: Please refer to the Kaletra® prescribing information for dosing recommendations based on body surface area and body weight. Neither lopinavir/ritonavir tablets nor oral solution should be administered once daily in combination with nevirapine. Nelfinavir* ↓Nelfinavir M8 Metabolite ↓Nelfinavir C min The appropriate doses of the combination of nevirapine and nelfinavir with respect to safety and efficacy have not been established. Saquinavir/Ritonavir The interaction between nevirapine and saquinavir/ritonavir has not been evaluated. The appropriate doses of the combination of nevirapine and saquinavir/ritonavir with respect to safety and efficacy have not been established. HIV Antiviral Agents: Non-Nucleoside Reverse Transcriptase Inhibitors (NNRTIs) Efavirenz* Etravirine Rilpivirine ↓ Efavirenz The appropriate doses of these combinations with respect to safety and efficacy have not been established. Plasma concentrations may be altered. Nevirapine should not be coadministered with another NNRTI as this combination has not been shown to be beneficial. Other Agents Analgesics: Methadone* ↓ Methadone Methadone levels were decreased; increased dosages may be required to prevent symptoms of opiate withdrawal. Methadone-maintained patients beginning nevirapine therapy should be monitored for evidence of withdrawal and methadone dose should be adjusted accordingly. Antiarrhythmics: Amiodarone, disopyramide, lidocaine Plasma concentrations may be decreased. Appropriate doses for this combination have not been established. Antibiotics: Clarithromycin* ↓ Clarithromycin ↑ 14-OH clarithromycin Clarithromycin exposure was significantly decreased by nevirapine; however, 14-OH metabolite concentrations were increased. Because clarithromycin active metabolite has reduced activity against Mycobacterium aviumintracellulare complex , overall activity against this pathogen may be altered. Alternatives to clarithromycin, such as azithromycin, should be considered. Rifabutin* ↑Rifabutin Rifabutin and its metabolite concentrations were moderately increased. Due to high intersubject variability, however, some patients may experience large increases in rifabutin exposure and may be at higher risk for rifabutin toxicity. Therefore, caution should be used in concomitant administration. Rifampin* ↓ Nevirapine Nevirapine and rifampin should not be administered concomitantly because decreases in nevirapine plasma concentrations may reduce the efficacy of the drug. Physicians needing to treat patients co-infected with tuberculosis and using a nevirapine-containing regimen may use rifabutin instead. Anticonvulsants: Carbamazepine, clonazepam, ethosuximide Plasma concentrations of nevirapine and the anticonvulsant may be decreased. Use with caution and monitor virologic response and levels of anticonvulsants. Antifungals: Fluconazole* ↑Nevirapine Because of the risk of increased exposure to nevirapine, caution should be used in concomitant administration, and patients should be monitored closely for nevirapine-associated adverse events. Ketoconazole* ↓ Ketoconazole Nevirapine and ketoconazole should not be administered concomitantly because decreases in ketoconazole plasma concentrations may reduce the efficacy of the drug. Itraconazole ↓ Itraconazole Nevirapine and itraconazole should not be administered concomitantly due to potential decreases in itraconazole plasma concentrations that may reduce efficacy of the drug. Antithrombotics: Warfarin Plasma concentrations may be increased. Potential effect on anticoagulation. Monitoring of anticoagulation levels is recommended. Calcium Channel Blockers: Diltiazem, nifedipine, verapamil Plasma concentrations may be decreased. Appropriate doses for these combinations have not been established. Cancer Chemotherapy: Cyclophosphamide Plasma concentrations may be decreased. Appropriate doses for this combination have not been established. Ergot Alkaloids: Ergotamine Plasma concentrations may be decreased. Appropriate doses for this combination have not been established. Immunosuppressants: Cyclosporine, tacrolimus, sirolimus Plasma concentrations may be decreased. Appropriate doses for these combinations have not been established. Opiate Agonists: Fentanyl Plasma concentrations may be decreased. Appropriate doses for this combination have not been established. Oral Contraceptives: Ethinyl Estradiol and Norethindrone* ↓ Ethinyl Estradiol ↓ Norethindrone Despite lower ethinyl estradiol and norethindrone exposures when coadministered with nevirapine, literature reports suggest that nevirapine has no effect on pregnancy rates among HIV-infected women on combined oral contraceptives. When coadministered with nevirapine ex
Adverse reactions
ADVERSE REACTIONS • Adult patients: The most common adverse reaction is rash. During the lead-in period with immediate-release nevirapine tablets, the incidence of Grade 2 or higher drug-related rash in adults is 3%. After the lead-in period the incidence of Grade 2 or higher drug-related rash in subjects taking nevirapine extended-release tablets is 3%. The incidence of Grade 2 or higher drug-related clinical hepatitis after the lead-in phase was 2%. ( 6.1 ) • Pediatric patients: The incidence of Grade 2 or higher drug-related rash was 1%. ( 6.1 ) To report SUSPECTED ADVERSE REACTIONS, contact Macleods Pharma USA, Inc. at 1-888-943-3210 or 1-855-926-3384 or FDA at 1-800-FDA-1088 or www.fda.gov/medwatch . 6.1 Clinical Trials Experience Because clinical trials are conducted under widely varying conditions, adverse reaction rates observed in the clinical trials of a drug cannot be directly compared to rates in the clinical trials of another drug and may not reflect the rates observed in clinical practice. Clinical Trial Experience in Adult Patients The most serious adverse reactions associated with nevirapine are hepatitis, hepatic failure, Stevens-Johnson syndrome, toxic epidermal necrolysis, and hypersensitivity reactions. Hepatitis/hepatic failure may be isolated or associated with signs of hypersensitivity which may include severe rash or rash accompanied by fever, general malaise, fatigue, muscle or joint aches, blisters, oral lesions, conjunctivitis, facial edema, eosinophilia, granulocytopenia, lymphadenopathy, or renal dysfunction [see Boxed Warning and Warnings and Precautions ( 5.1 , 5.2 )]. The most common clinical toxicity of nevirapine is rash, which can be severe or life-threatening [see Boxed Warning and Warnings and Precautions ( 5.2 )]. Rash occurs most frequently within the first 6 weeks of therapy. Rashes are usually mild to moderate, maculopapular erythematous cutaneous eruptions, with or without pruritus, located on the trunk, face and extremities. The safety database in nevirapine extended-release tablets clinical trials contains data from 800 subjects treated with nevirapine extended-release tablets and 654 subjects treated with immediate-release nevirapine tablets. Trial 1100.1486 (VERxVE) In Trial 1100.1486 (VERxVE), treatment-naïve subjects received a lead-in dose of immediate-release nevirapine tablets 200 mg once daily for 14 days (n=1,068) and then were randomized to receive either immediate-release nevirapine tablets 200 mg twice daily (n=506) or nevirapine extended-release tablets 400 mg once daily (n=505). All subjects received tenofovir + emtricitabine as background therapy. Subjects were enrolled with CD4 + counts less than 250 cells/mm 3 for women and less than 400 cells/mm3 for men [see Indications and Usage ( 1 )]. Data on potential symptoms of hepatic events were prospectively collected in this trial. The safety data include all subject visits up to the time of the last subject’s completion of the 96-week endpoint in the trial (mean observation period 98 weeks). After the lead-in period, the incidence of any hepatic event was 9% in the immediate-release nevirapine tablets group and 6% in the nevirapine extended-release tablets group; the incidence of symptomatic hepatic events (anorexia, jaundice, vomiting) was 3% and 2%, respectively. The incidence of GRADE 3 or 4 ALT/AST elevation was 8% in both the immediate-release nevirapine tablets group and nevirapine extended-release tablets group. Overall, there was a comparable incidence of symptomatic hepatic events among men and women enrolled in VERxVE. Severe or life-threatening rash considered to be related to nevirapine treatment occurred in 1% of subjects during the lead-in phase with immediate-release nevirapine tablets, and in 1% of subjects in either treatment group during the randomized phase. In addition, six cases of Stevens-Johnson syndrome were reported; all but one occurred within the first 30 days of nevirapine treatment. No Grade 2 or above adverse reactions judged to be related to treatment by the investigator occurred in more than 2% of subjects during the 14-day lead-in with immediate-release nevirapine tablets (200 mg once daily), except for rash which occurred in 4% of subjects. Adverse reactions of at least moderate intensity (Grades 2 or above) occurring in 2% or more of treatment-naïve subjects receiving either immediate-release nevirapine tablets or nevirapine extended-release tablets after randomization in Trial 1100.1486 are shown in Table 1. Table 1 Selected Clinical Adverse Drug Reactions* of at least Moderate Intensity (Grade 2 or above) Occurring in 2% or more of Adult Subjects - Week 96 Analysis of Trial 1100.1486 1 Adverse Drug Reaction Immediate-Release Nevirapine Tablets N=506 (%) Nevirapine Extended-Release Tablets N = 505 (%) Rash 2 4 5 Diarrhea 4 4 Headache 4 4 Clinical Hepatitis 3 4 2 Abdominal Pain 2 3 Arthralgia 2 2 Pyrexia 2 1 Nausea 2 1 Fatigue 2 2 * Excludes laboratory abnormalities reported as ADRs 1 Mean observation period 98 weeks. 2 Rash includes terms rash, rash maculo-papular, erythema nodosum, rash erythematous, rash papular, skin reaction, Stevens-Johnson syndrome, drug reaction with eosinophilia and systemic symptoms (DRESS). 3 Clinical hepatitis includes terms hepatitis, hepatotoxicity, hepatitis acute, liver disorder, hepatitis toxic, hepatic failure, jaundice. Laboratory Abnormalities Liver enzyme test abnormalities (AST, ALT) were observed in subjects receiving nevirapine extended-release tablets. Asymptomatic elevations in GGT occur frequently but are not a contraindication to continue therapy with nevirapine in the absence of elevations in other liver enzyme tests. Laboratory abnormalities that occurred in trial 1100.1486 are shown in Table 2. Table 2 Grade 2 to Grade 4 Laboratory Abnormalities that Represent a Worsening from Baseline Observed in at least 5% of Subjects in Either Treatment Group - Trial 1100.1486 Laboratory Parameter (unit) Limit Immediate-Release Nevirapine Tablets (%) (N=506) Nevirapine Extended-Release Tablets (%) (N=505) Chemistry SGPT/ALT (U/L) Grade 2 2.6-5.0 x ULN 13 10 Grade 3 5.1-10.0 x ULN 3 4 Grade 4 >10.0 x ULN 4 2 SGOT/AST (U/L) Grade 2 2.6-5.0 x ULN 9 7 Grade 3 5.1-10.0 x ULN 2 3 Grade 4 >10.0 x ULN 2 2 Amylase (U/L) Grade 2 1.6-2.0 x ULN 4 5 Grade 3 2.1-5.0 x ULN 4 2 Grade 4 >5.0 x ULN 0 <1 Phosphate (mg/dL) Grade 2 2.0-2.4 x ULN 38 33 Grade 3 1.0-1.9 x ULN 6 7 Grade 4 <1.0 x ULN <1 0 Hematology Neutrophils Grade 2 750-999/mm 3 7 4 Grade 3 500-749/mm 3 2 2 Grade 4 <500/mm 3 1 1 Lipids LDL (mg/dL) Grade 2 160-190 mg/dL 15 15 Grade 3 >190 mg/dL 5 5 Cholesterol (mg/dL) Grade 2 240-300 mg/dL 18 19 Grade 3 >300 mg/dL 4 3 Trial 1100.1526 (TRANxITION) In Trial 1100.1526 (TRANxITION) subjects on immediate-release nevirapine tablets 200 mg twice daily for at least 18 weeks were randomized to either receive nevirapine extended-release tablets 400 mg once daily (n=295) or remain on their immediate-release nevirapine tablets treatment (n=148). Adverse reactions observed for nevirapine extended-release tablets subjects (48 week analysis) were similar to those observed in trial 1100.1486, as displayed in Table 1. Clinical Trial Experience in Pediatric Patients Adverse reactions were assessed in Trial 1100.1518, an open-label, multiple-dose, non-randomized, cross-over trial to evaluate the safety and steady-state pharmacokinetic parameters of nevirapine extended-release tablets in HIV-1-infected pediatric subjects 3 to less than 18 years of age. Safety was further examined in an optional extension phase of the trial. Forty subjects who completed the pharmacokinetic part of the trial were treated with nevirapine extended-release tablets once daily in combination with other antiretrovirals for a median duration of 33 weeks. The most frequently reported adverse reactions related to nevirapine extended-release tablets in pediatric subjects were similar to those observed in adults. In pediatric sub
Mechanism of action
Mechanism of Action Nevirapine is an antiretroviral drug [see Microbiology (12.4) ]. Mechanism of Action Nevirapine is a non-nucleoside reverse transcriptase inhibitor (NNRTI) of HIV-1. Nevirapine binds directly to reverse transcriptase (RT) and blocks the RNA-dependent and DNA-dependent DNA polymerase activities by causing a disruption of the enzyme’s catalytic site. The activity of nevirapine does not compete with template or nucleoside triphosphates. HIV-2 RT and eukaryotic DNA polymerases (such as human DNA polymerases α, ß, γ, or δ) are not inhibited by nevirapine.