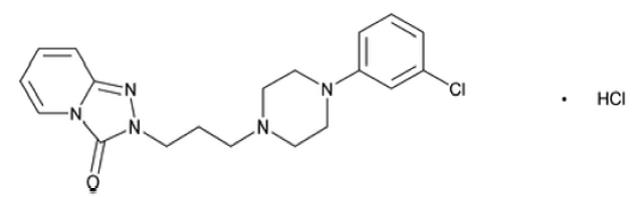
Trazodone. INDICATIONS AND USAGE Trazodone hydrochloride tablets, USP are a selective serotonin reuptake inhibitor indicated for the treatment of major…
Boxed warning
WARNING: SUICIDAL THOUGHTS and BEHAVIORS See full prescribing information for complete boxed warning. • Antidepresants increased the risk of suicidal thoughts and behaviors in pediatric and young adult patients ( 5.1 ) • Closely monitor for clinical worsening and emergence of suicidal thoughts and behaviors ( 5.1 ) • Trazodone hydrochloride tablets are not approved for use in pediatric patients ( 8.4 ) WARNING: SUICIDAL THOUGHTS AND BEHAVIORS Antidepressants increased the risk of suicidal thoughts and behavior in pediatric and young adult patients in short-term studies . Closely monitor all antidepressant-treated patients for clinical worsening, and for emergence of suicidal thoughts and behaviors [see Warnings and Precautions ( 5.1 )] . Trazodone hydrochloride tablets are not approved for use in pediatric patients [see Use in Specific Populations ( 8.4 )] .
INDICATIONS AND USAGE Trazodone hydrochloride tablets, USP are a selective serotonin reuptake inhibitor indicated for the treatment of major depressive disorder (MDD) ( 1 ). Trazodone hydrochloride tablets, USP are indicated for the treatment of major depressive disorder (MDD) in adults.
Dosage
DOSAGE AND ADMINISTRATION • Starting dose: 150 mg in divided doses daily. May be increased by 50 mg per day every three to four days. Maximum dose: 400 mg per day in divided doses ( 2 ). • Trazodone hydrochloride tablets should be taken shortly after a meal or light snack ( 2 ). • Tablets should be swallowed whole or broken in half along the score line, and should not be chewed or crushed( 2 ). • When discontinued, gradual dose reduction is recommended ( 2 ). 2.1 Dose Selection An initial dose of 150 mg/day in divided doses is suggested. The dosage should be initiated at a low-dose and increased gradually, noting the clinical response and any evidence of intolerance. Occurrence of drowsiness may require the administration of a major portion of the daily dose at bedtime or a reduction of dosage. The dose may be increased by 50 mg/day every 3 to 4 days. The maximum dose for outpatients usually should not exceed 400 mg/day in divided doses. Inpatients (i.e., more severely depressed patients) may be given up to but not in excess of 600 mg/day in divided doses Once an adequate response has been achieved, dosage may be gradually reduced, with subsequent adjustment depending on therapeutic response. 2.2 Important Administration Instructions Trazodone hydrochloride tablets can be swallowed whole or administered as a half tablet by breaking the tablet along the score line. Trazodone hydrochloride tablets should be taken shortly after a meal or light snack. 2.3 Screen for Bipolar Disorder Prior to Starting Trazodone Hydrochloride Tablets Prior to initiating treatment with trazodone hydrochloride tablets or another antidepressant, screen patients for a personal or family history of bipolar disorder, mania, or hypomania [see Warnings and Precautions ( 5.7 )]. 2.4 Switching to or from Monoamine Oxidase Inhibitor Antidepressant At least 14 days must elapse between discontinuation of a monoamine oxidase inhibitor (MAOI) antidepressant and initiation of trazodone hydrochloride tablets. In addition, at least 14 days must elapse after stopping trazodone hydrochloride tablets before starting an MAOI antidepressant [see Contraindications ( 4 ), Warnings and Precautions ( 5.2 )]. 2.5 Dosage Recommendations for Concomitant Use with Strong CYP3A4 Inhibitors or Inducers Coadministration with Strong CYP3A4 Inhibitors Consider reducing trazodone hydrochloride tablets dose based on tolerability when trazodone hydrochloride tablets are coadministered with a strong CYP3A4 inhibitor [see Drug Interactions ( 7.1 )]. Coadministration with Strong CYP3A4 Inducers Consider increasing trazodone hydrochloride tablets dose based on therapeutic response when trazodone hydrochloride tablets are coadministered with a strong CYP3A4 inducer [see Drug Interactions ( 7.1 )]. 2.6 Discontinuation of Treatment with Trazodone Hydrochloride Tablets Adverse reactions may occur upon discontinuation of trazodone hydrochloride tablets [See Warnings and Precautions ( 5.8 )]. Gradually reduce the dosage rather than stopping trazodone hydrochloride tablets abruptly whenever possible.
Warnings
WARNINGS AND PRECAUTIONS Serotonin Syndrome: Increased risk when co-administered with other serotonergic agents (e.g., SSRI, SNRI, triptans), but also when taken alone. If it occurs, discontinue trazodone and initiate supportive treatment ( 5.2 ). Cardiac Arrhythmias: Increases the QT interval. Avoid use with drugs that also increase the QT interval and in patients with risk factors for prolonged QT interval ( 5.3 ) Orthostatic Hypotension and Syncope: Warn patients of risk and symptoms of hypotension ( 5.4 ). Increased Risk of Bleeding: Concomitant use of aspirin, nonsteroidal anti-inflammatory drugs (NSAIDs), other antiplatelet drugs, warfarin, and other anticoagulants may increase this risk ( 5.5 ). Priapism: Cases of painful and prolonged penile erections and priapism have been reported. Immediate medical attention should be sought if signs and symptoms of prolonged penile erections or priapism are observed ( 5.6 ). Activation of Mania or Hypomania: Screen for bipolar disorder and monitor for mania or hypomania ( 5.7 ). Potential for Cognitive and Motor Impairment: Has potential to impair judgment, thinking, and motor skills. Advise patients to use caution when operating machinery ( 5.9 ). Angle-Closure Glaucoma: Avoid use of antidepressants, including trazodone, in patients with untreated anatomically narrow angles. ( 5.10 ). 5.1 Suicidal Thoughts and Behaviors in Pediatric and Young Adult Patients In pooled analyses of placebo-controlled trials of antidepressant drugs (SSRIs and other antidepressant classes) that included approximately 77,000 adult patients and over 4,400 pediatric patients, the incidence of suicidal thoughts and behaviors in pediatric and young adult patients was greater in antidepressant-treated patients than in placebo-treated patients. The drug-placebo differences in the number of cases of suicidal thoughts and behaviors per 1,000 patients treated are provided in Table 1. No suicides occurred in any of the pediatric studies. There were suicides in the adult studies, but the number was not sufficient to reach any conclusion about antidepressant drug effect on suicide. Table 1 Risk Differences of the Number of Cases of Suicidal Thoughts or Behaviors in the Pooled Placebo-Controlled Trials of Antidepressants in Pediatric and Adult Patients Age Range (years) Drug-Placebo Difference in Number of Patients of Suicidal Thoughts or Behaviors per 1,000 Patients Treated Increases Compared to Placebo < 18 14 additional patients 18 to 24 5 additional patients Decreases Compared to Placebo 25 to 64 1 fewer patient ≥ 65 6 fewer patients It is unknown whether the risk of suicidal thoughts and behaviors in pediatric and young adult patients extends to longer-term use, i.e., beyond four months. However, there is substantial evidence from placebo-controlled maintenance trials in adults with MDD that antidepressants delay the recurrence of depression. Monitor all antidepressant-treated patients for clinical worsening and emergence of suicidal thoughts and behaviors, especially during the initial few months of drug therapy and at times of dosage changes. Counsel family members or caregivers of patients to monitor for changes in behavior and to alert the healthcare provider. Consider changing the therapeutic regimen, including possibly discontinuing trazodone, in patients whose depression is persistently worse, or who are experiencing emergent suicidal thoughts or behaviors. 5.2 Serotonin Syndrome Serotonin-norepinephrine reuptake inhibitors (SNRIs) and SSRIs, including trazodone, can precipitate serotonin syndrome, a potentially life-threatening condition. The risk is increased with concomitant use of other serotonergic drugs (including triptans, tricyclic antidepressants, fentanyl, lithium, tramadol, tryptophan, buspirone, and St. John's Wort) and with drugs that impair metabolism of serotonin, i.e., MAOIs [see Contraindications ( 4 ), Drug Interactions ( 7.1 )] . Serotonin syndrome can also occur when these drugs are used alone. Serotonin syndrome signs and symptoms may include mental status changes (e.g., agitation, hallucinations, delirium, and coma), autonomic instability (e.g., tachycardia, labile blood pressure, dizziness, diaphoresis, flushing, hyperthermia), neuromuscular symptoms (e.g., tremor, rigidity, myoclonus, hyperreflexia, incoordination), seizures, and gastrointestinal symptoms (e.g., nausea, vomiting, diarrhea). The concomitant use of trazodone with MAOIs is contraindicated. In addition, do not initiate trazodone in a patient being treated with MAOIs such as linezolid or intravenous methylene blue. No reports involved the administration of methylene blue by other routes (such as oral tablets or local tissue injection). If it is necessary to initiate treatment with an MAOI such as linezolid or intravenous methylene blue in a patient taking trazodone, discontinue trazodone before initiating treatment with the MAOI [see Contraindications ( 4 ), Drug Interactions ( 7.1 )]. Monitor all patients taking trazodone for the emergence of serotonin syndrome. Discontinue treatment with trazodone and any concomitant serotonergic agents immediately if the above symptoms occur, and initiate supportive symptomatic treatment. If concomitant use of trazodone with other serotonergic drugs is clinically warranted, inform patients of the increased risk for serotonin syndrome and monitor for symptoms. 5.3 Cardiac Arrhythmias Clinical studies indicate that trazodone hydrochloride may be arrhythmogenic in patients with preexisting cardiac disease. Arrhythmias identified include isolated PVCs, ventricular couplets, tachycardia with syncope, and torsade de pointes. Postmarketing events, including torsade de pointes have been reported at doses of 100 mg or less with the immediate-release form of trazodone. Trazodone should also be avoided in patients with a history of cardiac arrhythmias, as well as other circumstances that may increase the risk of the occurrence of torsade de pointes and/or sudden death, including symptomatic bradycardia, hypokalemia or hypomagnesemia, and the presence of congenital prolongation of the QT interval. Trazodone is not recommended for use during the initial recovery phase of myocardial infarction. Caution should be used when administering trazodone to patients with cardiac disease and such patients should be closely monitored, since antidepressant drugs (including trazodone) may cause cardiac arrhythmias [see Adverse Reactions ( 6.2 )] . Trazodone prolongs the QT/QTc interval. The use of trazodone should be avoided in patients with known QT prolongation or in combination with other drugs that are inhibitors of CYP3A4 (e.g., itraconazole, clarithromycin, voriconazole), or known to prolong QT interval including Class 1A antiarrhythmics (e.g., quinidine, procainamide) or Class 3 antiarrhythmics (e.g., amiodarone, sotalol), certain antipsychotic medications (e.g., ziprasidone, chlorpromazine, thioridazine), and certain antibiotics (e.g., gatifloxacin). Concomitant administration of drugs may increase the risk of cardiac arrhythmia [see Drug Interactions ( 7.1 )]. 5.4 Orthostatic Hypotension and Syncope Hypotension, including orthostatic hypotension and syncope has been reported in patients receiving trazodone hydrochloride. Concomitant use with an antihypertensive may require a reduction in the dose of the antihypertensive drug. 5.5 Increased Risk of Bleeding Drugs that interfere with serotonin reuptake inhibition, including trazodone, increase the risk of bleeding events. Concomitant use of aspirin, nonsteroidal anti-inflammatory drugs (NSAIDS), other antiplatelet drugs, warfarin, and other anticoagulants may add to this risk. Case reports and epidemiological studies (case-control and cohort design) have demonstrated an association between use of drugs that interfere with serotonin reuptake and the occurrence of gastrointestinal bleeding. Bleeding events related to drugs that interfere with serotonin reuptake have ranged fr
Contraindications
CONTRAINDICATIONS Trazodone hydrochloride tablets are contraindicated in: Patients taking, or within 14 days of stopping, monoamine oxidase inhibitors (MAOIs), including MAOIs such as linezolid or intravenous methylene blue, because of an increased risk of serotonin syndrome [see Warnings and Precautions (5.2) , Drug Interactions (7.1) ]. Concomitant use of monoamine oxidase inhibitors (MAOIs), or use within 14 days of stopping MAOIs ( 4 ). Concomitant use of monoamine oxidase inhibitors (MAOIs), or use within 14 days of stopping MAOIs ( 4 ).
Drug interactions
DRUG INTERACTIONS CNS Depressants: Trazodone hydrochloride may enhance effects of alcohol, barbiturates, or other CNS depressants ( 7 ). CYP3A4 Inhibitors: Consider trazodone hydrochloride tablets dose reduction based on tolerability ( 2.5 , 7 ). CYP3A4 Inducers: Increase in trazodone hydrochloride tablets dosage may be necessary ( 2.5 , 7 ). Digoxin or Phenytoin: Monitor for increased digoxin or phenytoin serum levels ( 7 ). Warfarin: Monitor for increased or decreased prothrombin time ( 7 ). 7.1 Drugs Having Clinically Important Interactions with Trazodone Hydrochloride Table 3: Clinically Important Drug Interactions with Trazodone Hydrochloride Monoamine Oxidase Inhibitors (MAOIs) Clinical Impact: The concomitant use of MAOIs and serotonergic drugs including trazodone hydrochloride increases the risk of serotonin syndrome. Intervention: Trazodone hydrochloride is contraindicated in patients taking MAOIs, including MAOIs such as linezolid or intravenous methylene blue [see Contraindications ( 4 ), Dosage and Administration ( 2.3 , 2.4 ), and Warnings and Precautions ( 5.2 )]. Examples: isocarboxazid, moclobemide, phenelzine, selegiline, tranylcypromine Other Serotonergic Drugs Clinical Impact: The concomitant use of serotonergic drugs including trazodone hydrochloride and other serotonergic drugs increases the risk of serotonin syndrome. Intervention: Monitor patients for signs and symptoms of serotonin syndrome, particularly during trazodone hydrochloride initiation. If serotonin syndrome occurs, consider discontinuation of trazodone hydrochloride and/or concomitant serotonergic drugs [see Warnings and Precautions ( 5.2 )]. Examples: triptans, antidepressants (tricyclic and serotonin uptake inhibitors), fentanyl, lithium, tramadol, tryptophan, buspirone, and St. John's Wort Antiplatelet Agents and Anticoagulants Clinical Impact: Serotonin release by platelets plays an important role in hemostasis. The concurrent use of an antiplatelet agent or anticoagulant with trazodone hydrochloride may potentiate the risk of bleeding. Intervention: Inform patients of the increased risk of bleeding with the concomitant use of trazodone hydrochloride and antiplatelet agents and anticoagulants. For patients taking warfarin, carefully monitor the international normalized ratio (INR) when initiating or discontinuing trazodone hydrochloride [see Warnings and Precautions ( 5.5 )]. Examples: warfarin, rivaroxaban, dabigatran, clopidogrel Strong CYP3A4 Inhibitors Clinical Impact: The concomitant use of trazodone hydrochloride and strong CYP3A4 inhibitors increased the exposure of trazodone compared to the use of trazodone hydrochloride alone. Intervention: If trazodone hydrochloride is used with a potent CYP3A4 inhibitor, the risk of adverse reactions, including cardiac arrhythmias, may be increased and a lower dose of trazodone hydrochloride should be considered [see Dosage and Administration ( 2.5 ), Warnings and Precautions ( 5.3 )]. Examples: itraconazole, ketoconazole, clarithromycin, indinavir Strong CYP3A4 Inducers Clinical Impact: The concomitant use of trazodone hydrochloride and strong CYP3A4 inducers decreased the exposure of trazodone compared to the use of trazodone hydrochloride alone. Intervention: Patients should be closely monitored to see if there is a need for an increased dose of trazodone hydrochloride when taking CYP3A4 inducers [see Dosage and Administration ( 2.5 )]. Examples: rifampin, carbamazepine, phenytoin, St. John’s wort Digoxin and Phenytoin Clinical Impact: Digoxin and phenytoin are narrow therapeutic index drugs. Concomitant use of trazodone hydrochloride can increase digoxin or phenytoin concentrations. Intervention: Measure serum digoxin or phenytoin concentrations before initiating concomitant use of trazodone hydrochloride. Continue monitoring and reduce digoxin or phenytoin dose as necessary. Examples: digoxin, phenytoin Central Nervous System (CNS) Depressants Clinical Impact: Trazodone hydrochloride may enhance the response CNS depressants. Intervention: Patients should be counseled that trazodone hydrochloride may enhance the response to alcohol, barbiturates, and other CNS depressants. Examples: alcohol, barbiturates QT Interval Prolongation Clinical Impact: Concomitant use of drugs that prolong the QT interval may add to the QT effects of trazodone hydrochloride and increase the risk of cardiac arrhythmia. Intervention: Avoid the use of trazodone hydrochloride tablets in combination with other drugs known to prolong QTc [see Warnings and Precautions ( 5.3 )]. Examples: Class 1A antiarrhythmics: quinidine, procainamide, disopyramide; Class 3 antiarrhythmics: amiodarone, sotalol; Antipsychotics: ziprasidone, chlorpromazine, thioridazine; Antibiotics: gatifloxacin 7.1 Drugs Having Clinically Important Interactions with Trazodone Hydrochloride Table 3: Clinically Important Drug Interactions with Trazodone Hydrochloride Monoamine Oxidase Inhibitors (MAOIs) Clinical Impact: The concomitant use of MAOIs and serotonergic drugs including trazodone hydrochloride increases the risk of serotonin syndrome. Intervention: Trazodone hydrochloride is contraindicated in patients taking MAOIs, including MAOIs such as linezolid or intravenous methylene blue [see Contraindications ( 4 ), Dosage and Administration ( 2.3 , 2.4 ), and Warnings and Precautions ( 5.2 )]. Examples: isocarboxazid, moclobemide, phenelzine, selegiline, tranylcypromine Other Serotonergic Drugs Clinical Impact: The concomitant use of serotonergic drugs including trazodone hydrochloride and other serotonergic drugs increases the risk of serotonin syndrome. Intervention: Monitor patients for signs and symptoms of serotonin syndrome, particularly during trazodone hydrochloride initiation. If serotonin syndrome occurs, consider discontinuation of trazodone hydrochloride and/or concomitant serotonergic drugs [see Warnings and Precautions ( 5.2 )]. Examples: triptans, antidepressants (tricyclic and serotonin uptake inhibitors), fentanyl, lithium, tramadol, tryptophan, buspirone, and St. John's Wort Antiplatelet Agents and Anticoagulants Clinical Impact: Serotonin release by platelets plays an important role in hemostasis. The concurrent use of an antiplatelet agent or anticoagulant with trazodone hydrochloride may potentiate the risk of bleeding. Intervention: Inform patients of the increased risk of bleeding with the concomitant use of trazodone hydrochloride and antiplatelet agents and anticoagulants. For patients taking warfarin, carefully monitor the international normalized ratio (INR) when initiating or discontinuing trazodone hydrochloride [see Warnings and Precautions ( 5.5 )]. Examples: warfarin, rivaroxaban, dabigatran, clopidogrel Strong CYP3A4 Inhibitors Clinical Impact: The concomitant use of trazodone hydrochloride and strong CYP3A4 inhibitors increased the exposure of trazodone compared to the use of trazodone hydrochloride alone. Intervention: If trazodone hydrochloride is used with a potent CYP3A4 inhibitor, the risk of adverse reactions, including cardiac arrhythmias, may be increased and a lower dose of trazodone hydrochloride should be considered [see Dosage and Administration ( 2.5 ), Warnings and Precautions ( 5.3 )]. Examples: itraconazole, ketoconazole, clarithromycin, indinavir Strong CYP3A4 Inducers Clinical Impact: The concomitant use of trazodone hydrochloride and strong CYP3A4 inducers decreased the exposure of trazodone compared to the use of trazodone hydrochloride alone. Intervention: Patients should be closely monitored to see if there is a need for an increased dose of trazodone hydrochloride when taking CYP3A4 inducers [see Dosage and Administration ( 2.5 )]. Examples: rifampin, carbamazepine, phenytoin, St. John’s wort Digoxin and Phenytoin Clinical Impact: Digoxin and phenytoin are narrow therapeutic index drugs. Concomitant use of trazodone hydrochloride can increase digoxin or phenytoin concentrations. Intervention: Measure serum digoxin o
Adverse reactions
ADVERSE REACTIONS Most common adverse reactions (incidence ≥ 5% and twice that of placebo) are: edema, blurred vision, syncope, drowsiness, fatigue, diarrhea, nasal congestion, weight loss ( 6 ). To report SUSPECTED ADVERSE REACTIONS, contact AvKARE at 1-855-361-3993 or FDA at 1-800-FDA-1088 or www.fda.gov/medwatch. The following serious adverse reactions are described elsewhere in the labeling: Suicidal Thoughts and Behavior in Children, Adolescents and Young Adults [see Boxed Warning and Warnings and Precautions ( 5.1 )] Serotonin Syndrome [see Warnings and Precautions ( 5.2 )] Cardiac Arrythmias ( see Warnings and Precautions ( 5.3 )] Orthostatic Hypotension and Syncope [see Warnings and Precautions ( 5.4 )] Increased Risk of Bleeding [see Warnings and Precautions ( 5.5 )] Priapism [see Warnings and Precautions ( 5.6 )] Activation of Mania or Hypomania [see Warnings and Precautions ( 5.7 )] Discontinuation Syndrome [see Warnings and Precautions ( 5.8 )] Potential for Cognitive and Motor Impairment [see Warnings and Precautions ( 5.9 )] Angle-Closure Glaucoma [see Warnings and Precautions ( 5.10 )] Hyponatremia [see Warnings and Precautions ( 5.11 )] 6.1 Clinical Trials Experience Because clinical trials are conducted under widely varying conditions, adverse reaction rates observed in the clinical trials of a drug cannot be directly compared to rates in the clinical trials of another drug and may not reflect the rates observed in practice. Table 2 Common Adverse Reactions Occurring in ≥ 2% of Trazodone-treated Patients and Greater than the Rate of Placebo-Treated Patients as Observed in Controlled Clinical Studies Inpatients Outpatients Trazodone Placebo Trazodone Placebo 142 95 157 158 Allergic Skin Condition/Edema 3% 1% 7% 1% Autonomic Blurred Vision 6% 4% 15% 4% Constipation 7% 4% 8% 6% Dry Mouth 15% 8% 34% 20% Cardiovascular Hypertension 20% 1% 1% * Hypotension 7% 1% 4% 0 Syncope 3% 2% 5% 1% CNS Confusion 5% 0 6% 8% Decreased Concentration 3% 2% 1% 0 Disorientation 2% 0 * 0 Dizziness/Light-Headedness 20% 5% 28% 15% Drowsiness 24% 6% 41% 20% Fatigue 11% 4% 6% 3% Headache 10% 5% 20% 16% Nervousness 15% 11% 6% 8% Gastrointestinal Abdominal/Gastric Disorder 4% 4% 6% 4% Diarrhea 0 1% 5% 1% Nausea/Vomiting 10% 1% 13% 10% Musculoskeletal Aches/Pains 6% 3% 5% 3% Neurological Incoordination 5% 0 2% * Tremors 3% 1% 5% 4% Other Eyes Red/Tired/Itching 3% 0 0 0 Head Full-Heavy 3% 0 0 0 Malaise 3% 0 0 0 Nasal/Sinus Congestion 3% 0 6% 3% Weight Gain 1% 0 5% 2% Weight Loss * 3% 6% 3% Other adverse reactions occurring at an incidence of <2% with the use of trazodone hydrochloride in the controlled clinical studies: akathisia, allergic reaction, anemia, chest pain, delayed urine flow, early menses, flatulence, hallucinations/delusions, hematuria, hypersalivation, hypomania, impaired memory, impaired speech, impotence, increased appetite, increased libido, increased urinary frequency, missed periods, muscle twitches, numbness, paresthesia, retrograde ejaculation, shortness of breath, and tachycardia/palpitations. Occasional sinus bradycardia has occurred in long-term studies. 6.2 Postmarketing Experience The following adverse reactions have been identified during post-approval use of trazodone. Because these reactions are reported voluntarily from a population of uncertain size, it is not always possible to estimate their frequency or establish a causal relationship to drug exposure: Blood and lymphatic system disorders: hemolytic anemia, leukocytosis Cardiac disorders: cardiospasm, congestive heart failure, conduction block, orthostatic hypotension and syncope, palpitations, bradycardia, atrial fibrillation, myocardial infarction, cardiac arrest, arrhythmia, ventricular ectopic activity, including ventricular tachycardia and QT prolongation. Prolonged QT interval, torsade de pointes, and ventricular tachycardia have been reported at doses of 100 mg per day or less [see Warnings and Precautions ( 5.3 )]. Endocrine disorders: inappropriate ADH syndrome Eye disorders: diplopia Gastrointestinal disorders: increased salivation, nausea/vomiting General disorders and administration site conditions: chills, edema, unexplained death, weakness Hepatobiliary disorders: cholestasis, jaundice, hyperbilirubinemia, liver enzyme alterations Investigations: increased amylase Metabolism and nutrition disorders: methemoglobinemia Nervous system disorders: aphasia, ataxia, cerebrovascular accident, extrapyramidal symptoms, grand mal seizures, paresthesia, tardive dyskinesia, vertigo Psychiatric disorders: abnormal dreams, agitation, anxiety, hallucinations, insomnia, paranoid reaction, psychosis, stupor Renal and urinary disorders: urinary incontinence, urinary retention Reproductive system and breast disorders: breast enlargement or engorgement, clitorism, lactation, priapism [see Warnings and Precautions ( 5.6 )] Respiratory, thoracic and mediastinal disorders: apnea Skin and subcutaneous tissue disorders: alopecia, hirsutism, leukonychia, pruritus, psoriasis, rash, urticaria Vascular disorders: vasodilation To report SUSPECTED ADVERSE REACTIONS contact AvKARE at 1-855-361-3993; email drugsafety@avkare.com; or FDA at 1-800-FDA-1088 or www.fda.gov/medwatch. 6.2 Postmarketing Experience The following adverse reactions have been identified during post-approval use of trazodone. Because these reactions are reported voluntarily from a population of uncertain size, it is not always possible to estimate their frequency or establish a causal relationship to drug exposure: Blood and lymphatic system disorders: hemolytic anemia, leukocytosis Cardiac disorders: cardiospasm, congestive heart failure, conduction block, orthostatic hypotension and syncope, palpitations, bradycardia, atrial fibrillation, myocardial infarction, cardiac arrest, arrhythmia, ventricular ectopic activity, including ventricular tachycardia and QT prolongation. Prolonged QT interval, torsade de pointes, and ventricular tachycardia have been reported at doses of 100 mg per day or less [see Warnings and Precautions ( 5.3 )]. Endocrine disorders: inappropriate ADH syndrome Eye disorders: diplopia Gastrointestinal disorders: increased salivation, nausea/vomiting General disorders and administration site conditions: chills, edema, unexplained death, weakness Hepatobiliary disorders: cholestasis, jaundice, hyperbilirubinemia, liver enzyme alterations Investigations: increased amylase Metabolism and nutrition disorders: methemoglobinemia Nervous system disorders: aphasia, ataxia, cerebrovascular accident, extrapyramidal symptoms, grand mal seizures, paresthesia, tardive dyskinesia, vertigo Psychiatric disorders: abnormal dreams, agitation, anxiety, hallucinations, insomnia, paranoid reaction, psychosis, stupor Renal and urinary disorders: urinary incontinence, urinary retention Reproductive system and breast disorders: breast enlargement or engorgement, clitorism, lactation, priapism [see Warnings and Precautions ( 5.6 )] Respiratory, thoracic and mediastinal disorders: apnea Skin and subcutaneous tissue disorders: alopecia, hirsutism, leukonychia, pruritus, psoriasis, rash, urticaria Vascular disorders: vasodilation To report SUSPECTED ADVERSE REACTIONS contact AvKARE at 1-855-361-3993; email drugsafety@avkare.com; or FDA at 1-800-FDA-1088 or www.fda.gov/medwatch.
Mechanism of action
CLINICAL PHARMACOLOGY 12.1 Mechanism of Action The mechanism of trazodone’s antidepressant action is not fully understood, but is thought to be related to its enhancement of serotonergic activity in the CNS. Trazodone is both a selective serotonin reuptake inhibitor (SSRI) and a 5HT 2 receptor antagonist and the net result of this action on serotonergic transmission and its role in trazodone’s antidepressant effect is unknown. 12.2 Pharmacodynamics Preclinical studies have shown that trazodone selectively inhibits neuronal reuptake of serotonin (Ki = 367 nM) and acts as an antagonist at 5-HT 2A (Ki = 35.6 nM) serotonin receptors. Trazodone is also an antagonist at several other monoaminergic receptors including 5-HT 2B (Ki = 78.4 nM), 5-HT 2C (Ki = 224 nM), α 1A (Ki = 153 nM), α 2C (Ki = 155 nM) receptors and it is a partial agonist at 5 HT 1A (Ki = 118 nM) receptor. Trazodone antagonizes alpha 1-adrenergic receptors, a property which may be associated with postural hypotension. 12.3 Pharmacokinetics Absorption In humans, trazodone hydrochloride is absorbed after oral administration without selective localization in any tissue. When trazodone hydrochloride is taken shortly after ingestion of food, there may be an increase in the amount of drug absorbed, a decrease in maximum concentration and a lengthening in the time to maximum concentration. Peak plasma levels occur approximately one hour after dosing when trazodone hydrochloride is taken on an empty stomach or 2 hours after dosing when taken with food. Metabolism In vitro studies in human liver microsomes show that trazodone is metabolized, via oxidative cleavage, to an active metabolite, m- chlorophenylpiperazine (mCPP) by CYP3A4. Other metabolic pathways that may be involved in the metabolism of trazodone have not been well characterized. Trazodone is extensively metabolized; less than 1% of an oral dose is excreted unchanged in the urine. Elimination In some patients trazodone may accumulate in the plasma. Protein Binding Trazodone is 89 to 95% protein bound in vitro at concentrations attained with therapeutic doses in humans.