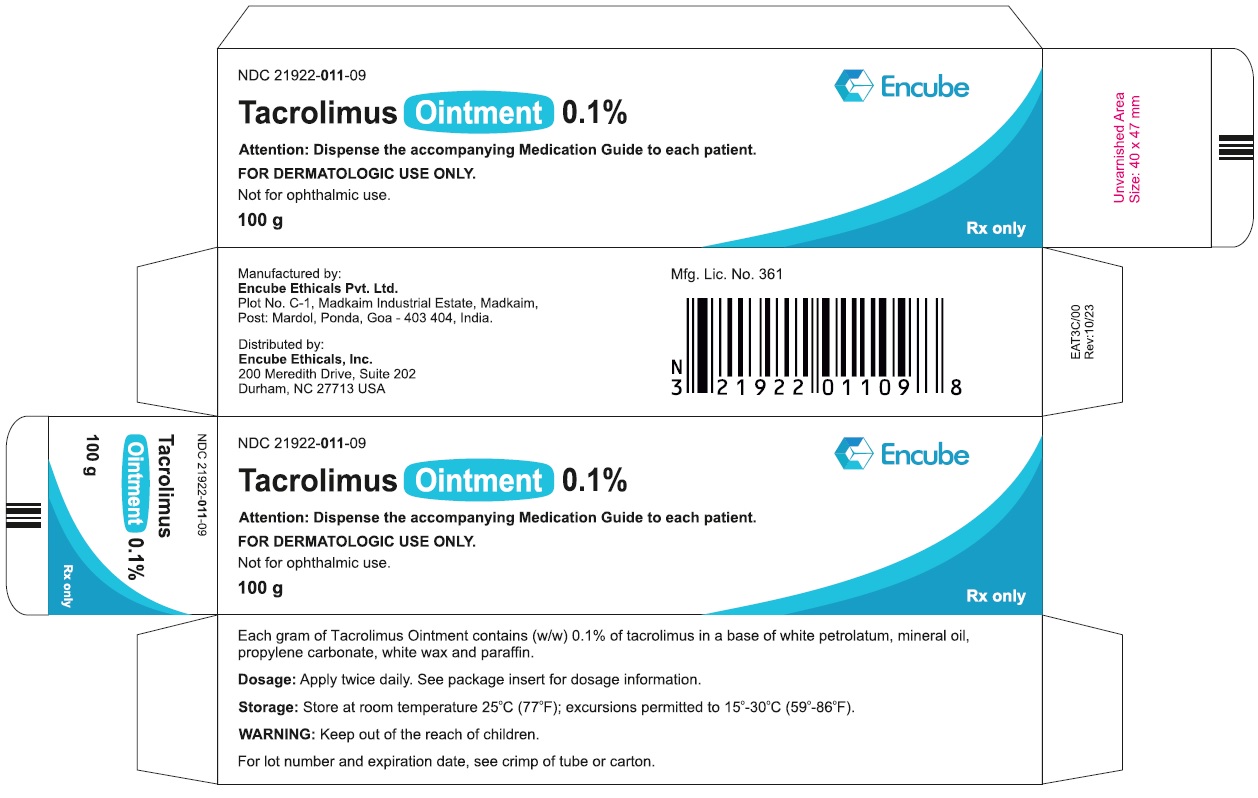
Tacrolimus Ointment 0.1%. INDICATIONS AND USAGE Tacrolimus ointment, both 0.03% and 0.1% for adults, and only 0.03% for children aged 2 to 15 years, is indicated as…
Boxed warning
WARNING Long-term Safety of Topical Calcineurin Inhibitors Has Not Been Established Although a causal relationship has not been established, rare cases of malignancy (e.g., skin and lymphoma) have been reported in patients treated with topical calcineurin inhibitors, including tacrolimus ointment. Therefore: • Continuous long-term use of topical calcineurin inhibitors, including tacrolimus ointment, in any age group should be avoided, and application limited to areas of involvement with atopic dermatitis. • Tacrolimus ointment is not indicated for use in children less than 2 years of age. Only 0.03% tacrolimus ointment is indicated for use in children 2-15 years of age.
INDICATIONS AND USAGE Tacrolimus ointment, both 0.03% and 0.1% for adults, and only 0.03% for children aged 2 to 15 years, is indicated as second-line therapy for the short-term and non-continuous chronic treatment of moderate to severe atopic dermatitis in non-immunocompromised adults and children who have failed to respond adequately to other topical prescription treatments for atopic dermatitis, or when those treatments are not advisable. Tacrolimus ointment is not indicated for children younger than 2 years of age (see boxed WARNING , WARNINGS and PRECAUTIONS : Pediatric Use ).
Dosage
DOSAGE AND ADMINISTRATION ADULT Tacrolimus ointment 0.1% Apply a thin layer of tacrolimus ointment to the affected skin twice daily. The minimum amount should be rubbed in gently and completely to control signs and symptoms of atopic dermatitis. Stop using when signs and symptoms of atopic dermatitis resolve. If signs and symptoms (e.g. itch, rash, and redness) do not improve within 6 weeks, patients should be re-examined by their healthcare provider to confirm the diagnosis of atopic dermatitis. Continuous long-term use of topical calcineurin inhibitors, including tacrolimus ointment should be avoided, and application should be limited to areas of involvement with atopic dermatitis. The safety of tacrolimus ointment under occlusion, which may promote systemic exposure, has not been evaluated. Tacrolimus ointment should not be used with occlusive dressings.
Warnings
Prolonged systemic use of calcineurin inhibitors for sustained immunosuppression in animal studies and transplant patients following systemic administration has been associated with an increased risk of infections, lymphomas, and skin malignancies. These risks are associated with the intensity and duration of immunosuppression. Based on the information above and the mechanism of action, there is a concern about potential risk with the use of topical calcineurin inhibitors, including tacrolimus ointment. While a causal relationship has not been established, rare cases of skin malignancy and lymphoma have been reported in patients treated with topical calcineurin inhibitors, including tacrolimus ointment. Therefore: Tacrolimus ointment should not be used in immunocompromised adults and children. If signs and symptoms of atopic dermatitis do not improve within 6 weeks, patients should be re- examined by their healthcare provider and their diagnosis be confirmed (see PRECAUTIONS : General ). The safety of tacrolimus ointment has not been established beyond one year of non-continuous use. (See CLINICAL PHARMACOLOGY , boxed WARNING , INDICATIONS AND USAGE , and DOSAGE AND ADMINISTRATION ).
Contraindications
CONTRAINDICATIONS Tacrolimus ointment is contraindicated in patients with a history of hypersensitivity to tacrolimus or any other component of the ointment.
Drug interactions
Drug Interactions Formal topical drug interaction studies with tacrolimus ointment have not been conducted. Based on its extent of absorption, interactions of tacrolimus ointment with systemically administered drugs are unlikely to occur but cannot be ruled out (see CLINICAL PHARMACOLOGY ). The concomitant administration of known CYP3A4 inhibitors in patients with widespread and/or erythrodermic disease should be done with caution. Some examples of such drugs are erythromycin, itraconazole, ketoconazole, fluconazole, calcium channel blockers and cimetidine.
Adverse reactions
ADVERSE REACTIONS No phototoxicity and no photoallergenicity were detected in clinical studies with 12 and 216 normal volunteers, respectively. One out of 198 normal volunteers showed evidence of sensitization in a contact sensitization study. In three 12 week randomized vehicle-controlled studies and four safety studies, 655 and 9,163 patients respectively, were treated with tacrolimus ointment. The duration of follow-up for adult and pediatric patients in the safety studies is tabulated below. Duration of Follow-up in Four Open-label Safety Studies Time on Study Adult Pediatrics Total < 1 year 4682 4481 9163 ≥ 1 year 1185 1349 2534 ≥ 2 years 200 275 475 ≥ 3 years 118 182 300 The following table depicts the adjusted incidence of adverse events pooled across the 3 identically designed 12-week controlled studies for patients in vehicle, tacrolimus ointment 0.03%, and tacrolimus ointment 0.1% treatment groups. The table also depicts the unadjusted incidence of adverse events in four safety studies, regardless of relationship to study drug. Incidence of Treatment Emergent Adverse Events 12-Week, Randomized, Double-Blind, Phase 3 Studies 12-Week Adjusted Incidence Rate (%) Open-Label Studies (up to 3 years) 0.1% and 0.03% Tacrolimus ointment Incidence Rate (%) Adult Pediatric Adult Pediatric Total Vehicle (n=212) % 0.03% Tacrolimus ointment (n=210) % 0.1% Tacrolimus ointment (n=209) % Vehicle (n=116) % 0.03% Tacrolimus ointment (n=118) % (n=4682) % (n=4481) % (n=9163) % Skin Burning* 26 46 58 29 43 28 20 24 Pruritus* 37 46 46 27 41 25 19 22 Flu-like symptoms* 19 23 31 25 28 22 34 28 Allergic Reaction 8 12 6 8 4 9 13 11 Skin Erythema 20 25 28 13 12 12 7 9 Headache* 11 20 19 8 5 13 9 11 Skin Infection 11 12 5 14 10 9 16 12 Fever 4 4 1 13 21 2 14 8 Infection 1 1 2 9 7 6 10 8 Cough Increased 2 1 1 14 18 3 10 6 Asthma 4 6 4 6 6 4 13 8 Herpes Simplex 4 4 4 2 0 4 3 3 Eczema Herpeticum 0 1 1 0 2 0 0 0 Pharyngitis 3 3 4 11 6 4 12 8 Accidental Injury 4 3 6 3 6 6 8 7 Pustular Rash 2 3 4 3 2 2 7 5 Folliculitis* 1 6 4 0 2 4 2 3 Rhinitis 4 3 2 2 6 2 4 3 Otitis Media 4 0 1 6 12 2 11 6 Sinusitis* 1 4 2 8 3 6 7 6 Diarrhea 3 3 4 2 5 2 4 3 Urticaria 3 3 6 1 1 3 4 4 Lack of Drug Effect 1 1 0 1 1 6 6 6 Bronchitis 0 2 2 3 3 4 4 4 Vomiting 0 1 1 7 6 1 4 3 Maculopapular Rash 2 2 2 3 0 2 1 1 Rash* 1 5 2 4 2 2 3 3 Abdominal Pain 3 1 1 2 3 1 3 2 Fungal Dermatitis 0 2 1 3 0 2 4 3 Gastroenteritis 1 2 2 3 0 2 4 3 Alcohol Intolerance* 0 3 7 0 0 4 0 2 Acne* 2 4 7 1 0 3 2 3 Sunburn 1 2 1 0 0 2 1 1 Skin Disorder 2 2 1 1 4 2 2 2 Conjunctivitis 0 2 2 2 1 3 3 3 Pain 1 2 1 0 1 2 1 2 Vesiculobullous Rash* 3 3 2 0 4 2 1 1 Lymphadenopathy 2 2 1 0 3 1 2 1 Nausea 4 3 2 0 1 2 1 2 Skin Tingling* 2 3 8 1 2 2 1 1 Face Edema 2 2 1 2 1 1 1 1 Dyspepsia* 1 1 4 0 0 2 2 2 Dry Skin 7 3 3 0 1 1 1 1 Hyperesthesia* 1 3 7 0 0 2 0 1 Skin Neoplasm Benign† 1 1 1 0 0 1 2 2 Back Pain* 0 2 2 1 1 3 0 2 Peripheral Edema 2 4 3 0 0 2 0 1 Varicella Zoster/Herpes Zoster*‡ 0 1 0 0 5 1 2 2 Contact Dermatitis 1 3 3 3 4 2 2 2 Asthenia 1 2 3 0 0 1 0 1 Pneumonia 0 1 1 2 0 1 3 2 Eczema 2 2 2 0 0 1 0 1 Insomnia 3 4 3 1 1 2 0 1 Exfoliative Dermatitis 3 3 1 0 0 0 1 0 Dysmenorrhea 2 4 4 0 0 2 1 1 Periodontal Abscess 1 0 1 0 0 1 1 1 Myalgia* 0 3 2 0 0 2 1 1 Cyst* 0 1 3 0 0 1 0 1 Cellulitis 1 1 1 0 0 1 1 1 Exacerbation of Untreated Area 1 0 1 1 0 1 1 1 Procedural Complication 1 0 0 1 0 1 1 1 Hypertension 0 0 1 0 0 2 0 1 Tooth Disorder 0 1 1 1 0 2 1 1 Arthralgia 1 1 3 2 0 2 1 2 Depression 1 2 1 0 0 1 0 1 Paresthesia 1 3 3 0 0 2 1 2 Alopecia 0 1 1 0 0 1 1 1 Urinary Tract Infection 0 0 1 0 0 2 1 2 Ear Pain 1 0 1 0 1 0 1 1 * May be reasonably associated with the use of this drug product † Generally “warts”. ‡ All the herpes zoster cases in the pediatric 12- week study and the majority of cases in the open- label pediatric studies were reported as chicken pox. Other adverse events which occurred at an incidence between 0.2% and less than 1% in clinical studies in the above table include: abnormal vision, abscess, anaphylactoid reaction, anemia, anorexia, anxiety, arthritis, arthrosis, bilirubinemia, blepharitis, bone disorder, breast neoplasm benign, bursitis, cataract NOS, chest pain, chills, colitis, conjunctival edema, constipation, cramps, cutaneous moniliasis, cystitis, dehydration, dizziness, dry eyes, dry mouth/nose, dyspnea, ear disorder, ecchymosis, edema, epistaxis, eye pain, furunculosis, gastritis, gastrointestinal disorder, hernia, hypercholesterolemia, hypertonia, hypothyroidism, joint disorder, laryngitis, leukoderma, lung disorder, malaise, migraine, moniliasis, mouth ulceration, nail disorder, neck pain, neoplasm benign, oral moniliasis, otitis externa, photosensitivity reaction, rectal disorder, seborrhea, skin carcinoma, skin discoloration, skin hypertrophy, skin ulcer, stomatitis, tendon disorder, thinking abnormal, tooth caries, sweating, syncope, tachycardia, taste perversion, unintended pregnancy, vaginal moniliasis, vaginitis, valvular heart disease, vasodilatation, and vertigo. Post-Marketing Events The following adverse reactions have been identified during postapproval use of tacrolimus ointment. Because these reactions are reported voluntarily from a population of uncertain size, it is not always possible to reliably estimate their frequency or establish a causal relationship to drug exposure. CNS Seizures Neoplasms Lymphomas, basal cell carcinoma, squamous cell carcinoma, malignant melanoma Infections Bullous impetigo, osteomyelitis, septicemia Renal Acute renal failure in patients with or without Netherton’s syndrome, renal impairment Skin Rosacea, application site edema
Mechanism of action
CLINICAL PHARMACOLOGY Mechanism of Action The mechanism of action of tacrolimus in atopic dermatitis is not known. While the following have been observed, the clinical significance of these observations in atopic dermatitis is not known. It has been demonstrated that tacrolimus inhibits T-lymphocyte activation by first binding to an intracellular protein, FKBP-12. A complex of tacrolimus-FKBP-12, calcium, calmodulin, and calcineurin is then formed and the phosphatase activity of calcineurin is inhibited. This effect has been shown to prevent the dephosphorylation and translocation of nuclear factor of activated T-cells (NF-AT), a nuclear component thought to initiate gene transcription for the formation of lymphokines (such as interleukin-2, gamma interferon). Tacrolimus also inhibits the transcription for genes which encode IL-3, IL-4, IL-5, GM-CSF, and TNF-α, all of which are involved in the early stages of T-cell activation. Additionally, tacrolimus has been shown to inhibit the release of pre-formed mediators from skin mast cells and basophils, and to down regulate the expression of FcεRI on Langerhans cells. Pharmacokinetics Absorption The pooled results from three pharmacokinetic studies in 88 adult atopic dermatitis patients indicate that tacrolimus is minimally absorbed after the topical application of tacrolimus ointment. Peak tacrolimus blood concentrations ranged from undetectable to 20 ng/mL after single or multiple doses of 0.03% and 0.1% tacrolimus ointment, with 85% (75/88) of the patients having peak blood concentrations less than 2 ng/mL. In general as treatment continued, systemic exposure declined as the skin returned to normal. In clinical studies with periodic blood sampling, a similar distribution of tacrolimus blood levels was also observed in adult patients, with 90% (1,253/1,391) of patients having a blood concentration less than 2 ng/mL. The absolute bioavailability of tacrolimus from tacrolimus ointment in atopic dermatitis patients is approximately 0.5%. In adults with an average of 53% BSA treated, exposure (AUC) of tacrolimus from tacrolimus ointment is approximately 30-fold less than that seen with oral immunosuppressive doses in kidney and liver transplant patients. Mean peak tacrolimus blood concentrations following oral administration (0.3 mg/kg/day) in adult kidney transplant (n=26) and liver transplant (n=17) patients are 24.2±15.8 ng/mL and 68.5±30.0 ng/mL, respectively. The lowest tacrolimus blood level at which systemic effects (e.g., immunosuppression) can be observed is not known. Systemic levels of tacrolimus have also been measured in pediatric patients (see Special Populations: Pediatrics ). Distribution The plasma protein binding of tacrolimus is approximately 99% and is independent of concentration over a range of 5 to 50 ng/mL. Tacrolimus is bound mainly to albumin and alpha-1-acid glycoprotein, and has a high level of association with erythrocytes. The distribution of tacrolimus between whole blood and plasma depends on several factors, such as hematocrit, temperature at the time of plasma separation, drug concentration, and plasma protein concentration. In a US study, the ratio of whole blood concentration to plasma concentration averaged 35 (range 12 to 67). There was no evidence based on blood concentrations that tacrolimus accumulates systemically upon intermittent topical application for periods of up to 1 year. As with other topical calcineurin inhibitors, it is not known whether tacrolimus is distributed into the lymphatic system. Metabolism Tacrolimus is extensively metabolized by the mixed-function oxidase system, primarily the cytochrome P-450 system (CYP3A). A metabolic pathway leading to the formation of 8 possible metabolites has been proposed. Demethylation and hydroxylation were identified as the primary mechanisms of biotransformation in vitro. The major metabolite identified in incubations with human liver microsomes is 13-demethyl tacrolimus. In in vitro studies, a 31-demethyl metabolite has been reported to have the same activity as tacrolimus. Excretion The mean clearance following IV administration of tacrolimus is 0.04, 0.083 and 0.053 L/hr/kg in healthy volunteers, adult kidney transplant patients and adult liver transplant patients, respectively. In man, less than 1% of the dose administered is excreted unchanged in urine. In a mass balance study of IV administered radiolabeled tacrolimus to 6 healthy volunteers, the mean recovery of radiolabel was 77.8 ± 12.7%. Fecal elimination accounted for 92.4 ± 1.0% and the elimination half-life based on radioactivity was 48.1 ± 15.9 hours whereas it was 43.5 ± 11.6 hours based on tacrolimus concentrations. The mean clearance of radiolabel was 0.029 ± 0.015 L/hr/kg and clearance of tacrolimus was 0.029 ± 0.009 L/hr/kg. When administered PO, the mean recovery of the radiolabel was 94.9 ± 30.7%. Fecal elimination accounted for 92.6 ± 30.7%, urinary elimination accounted for 2.3 ± 1.1% and the elimination half-life based on radioactivity was 31.9 ± 10.5 hours whereas it was 48.4 ± 12.3 hours based on tacrolimus concentrations. The mean clearance of radiolabel was 0.226 ± 0.116 L/hr/kg and clearance of tacrolimus 0.172 ± 0.088 L/hr/kg. Special Populations Pediatrics In a pharmacokinetic study of 14 pediatric atopic dermatitis patients, between the ages of 2 to 5 years, peak blood concentrations of tacrolimus ranged from undetectable to 14.8 ng/mL after single or multiple doses of 0.03% tacrolimus ointment, with 86% (12/14) of patients having peak blood concentrations below 2 ng/mL throughout the study. The highest peak concentration was observed in one patient with 82% BSA involvement on day 1 following application of 0.03% tacrolimus ointment. The peak concentrations for this subject were 14.8 ng/mL on day 1 and 4.1 ng/mL on day 14. Mean peak tacrolimus blood concentrations following oral administration in pediatric liver transplant patients (n = 9) were 48.4± 27.9 ng/mL. In a similar pharmacokinetic study with 61 enrolled pediatric patients (ages 6 to 12 years) with atopic dermatitis, peak tacrolimus blood concentrations ranged from undetectable to 5.3 ng/mL after single or multiple doses of 0.1% tacrolimus ointment, with 91% (52/57) of evaluable patients having peak blood concentrations below 2 ng/mL throughout the study period. When detected, systemic exposure generally declined as treatment continued. In clinical studies with periodic blood sampling, a similar distribution of tacrolimus blood levels was also observed, with 98% (509/522) of pediatric patients having a blood concentration below 2 ng/mL. Renal Insufficiency The effect of renal insufficiency on the pharmacokinetics of topically administered tacrolimus has not been evaluated. The mean clearance of IV administered tacrolimus in patients with renal dysfunction was similar to that of normal volunteers. On the basis of this information dose-adjustment is not expected to be needed. Hepatic Insufficiency The effect of hepatic insufficiency on the pharmacokinetics of topically administered tacrolimus has not been evaluated but dose-adjustment is not expected to be needed.