20 ML milrinone lactate 1 MG/ML Injection
Managing this medication for someone you care for? Eleplan keeps diagnoses, medications and appointments in one plan.
Start free with EleplanClinical drug
20 ML milrinone lactate 1 MG/ML Injection
1 MG/ML · Injection · injection
A form of milrinone →
20 ML milrinone lactate 1 MG/ML Injection — Phosphodiesterase inhibitors. INDICATIONS AND USAGE Milrinone Lactate Injection, USP and Milrinone Lactate in 5% Dextrose Injection are indicated for the short-term intravenous…
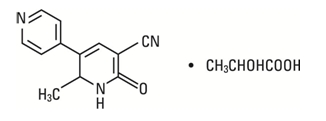
Active ingredient
Classification
Phosphodiesterase inhibitorsPhosphodiesterase 3 Inhibitor
Real-world adverse events (FAERS)
Drug Ineffective89Hypotension16Renal Failure13Cardiac Failure12Dyspnoea11Cardiac Arrest10Off Label Use10Ventricular Tachycardia10
Indications
INDICATIONS AND USAGE Milrinone Lactate Injection, USP and Milrinone Lactate in 5% Dextrose Injection are indicated for the short-term intravenous treatment of patients with acute decompensated heart failure. Patients receiving milrinone should be observed closely with appropriate electrocardiographic equipment. The facility for immediate treatment of potential cardiac events, which may include life threatening ventricular arrhythmias, must be available. The majority of experience with intravenous milrinone has been in patients receiving digoxin and diuretics. There is no experience in controlled trials with infusions of milrinone for periods exceeding 48 hours.
Dosage
DOSAGE AND ADMINISTRATION A loading dose of Milrinone Lactate Injection ( 1 mg [base]/mL ) should be administered followed by a continuous infusion (maintenance dose) according to the following guidelines: Loading Dose 50 mcg/kg: Administer slowly over 10 minutes. The table below shows the loading dose in milliliters (mL) of milrinone (1 mg/mL) by patient body weight (kg). Loading Dose (mL) Using 1 mg/mL Concentration Patient Body Weight (kg) kg 30 40 50 60 70 80 90 100 110 120 mL 1.5 2 2.5 3 3.5 4 4.5 5 5.5 6 The loading dose may be given undiluted, but diluting to a rounded total volume of 10 or 20 mL (see Maintenance Dose for diluents) may simplify the visualization of the injection rate. Maintenance Dose Maintenance Dose Infusion Rate Total Daily Dose (24 Hours) Minimum 0.375 mcg/kg/min 0.59 mg/kg Administer as a continuous intravenous infusion Standard 0.5 mcg/kg/min 0.77 mg/kg Maximum 0.75 mcg/kg/min 1.13 mg/kg Milrinone drawn from vials should be diluted prior to maintenance dose administration. The diluents that may be used are 0.45% Sodium Chloride Injection, USP, 0.9% Sodium Chloride Injection, USP, or 5% Dextrose Injection, USP. The table below shows the volume of diluent in milliliters (mL) that must be used to achieve 200 mcg/mL concentration for infusion, and the resultant total volumes. Desired Infusion Concentration mcg/mL Milrinone 1 mg/mL (mL) Diluent (mL) Total Volume (mL) 200 10 40 50 200 20 80 100 The infusion rate should be adjusted according to hemodynamic and clinical response. Patients should be closely monitored. In controlled clinical studies, most patients showed an improvement in hemodynamic status as evidenced by increases in cardiac output and reductions in pulmonary capillary wedge pressure. Note: See “ Dosage Adjustment in Renally Impaired Patients ” Dosage may be titrated to the maximum hemodynamic effect and should not exceed 1.13 mg/kg/day. Duration of therapy should depend upon patient responsiveness. The maintenance dose in mL/hr by patient body weight (kg) may be determined by reference to the following table. Milrinone Infusion Rate (mL/hr) Using 200 mcg/mL Concentration Maintenance Dose (mcg/kg/min) Patient Body Weight (kg) 30 40 50 60 70 80 90 100 110 120 0.375 3.4 4.5 5.6 6.8 7.9 9 10.1 11.3 12.4 13.5 0.4 3.6 4.8 6 7.2 8.4 9.6 10.8 12 13.2 14.4 0.5 4.5 6 7.5 9 10.5 12 13.5 15 16.5 18 0.6 5.4 7.2 9 10.8 12.6 14.4 16.2 18 19.8 21.6 0.7 6.3 8.4 10.5 12.6 14.7 16.8 18.9 21 23.1 25.2 0.75 6.8 9 11.3 13.5 15.8 18 20.3 22.5 24.8 27 When administering milrinone lactate by continuous infusion, it is advisable to use a calibrated electronic infusion device. Intravenous drug products should be inspected visually and should not be used if particulate matter or discoloration is present. Dosage Adjustment in Renally Impaired Patients Data obtained from patients with severe renal impairment (creatinine clearance = 0 to 30 mL/min) but without congestive heart failure have demonstrated that the presence of renal impairment significantly increases the terminal elimination half-life of milrinone. Reductions in infusion rate may be necessary in patients with renal impairment. For patients with clinical evidence of renal impairment, the recommended infusion rate can be obtained from the following table: Creatinine Clearance (mL/min/1.73 m 2 ) Infusion Rate (mcg/kg/min) 5 0.2 10 0.23 20 0.28 30 0.33 40 0.38 50 0.43 Loading Dose 50 mcg/kg: Administer slowly over 10 minutes. The table below shows the loading dose in milliliters (mL) of milrinone (1 mg/mL) by patient body weight (kg). Loading Dose (mL) Using 1 mg/mL Concentration Patient Body Weight (kg) kg 30 40 50 60 70 80 90 100 110 120 mL 1.5 2 2.5 3 3.5 4 4.5 5 5.5 6 The loading dose may be given undiluted, but diluting to a rounded total volume of 10 or 20 mL (see Maintenance Dose for diluents) may simplify the visualization of the injection rate. Maintenance Dose Maintenance Dose Infusion Rate Total Daily Dose (24 Hours) Minimum 0.375 mcg/kg/min 0.59 mg/kg Administer as a continuous intravenous infusion Standard 0.5 mcg/kg/min 0.77 mg/kg Maximum 0.75 mcg/kg/min 1.13 mg/kg Milrinone drawn from vials should be diluted prior to maintenance dose administration. The diluents that may be used are 0.45% Sodium Chloride Injection, USP, 0.9% Sodium Chloride Injection, USP, or 5% Dextrose Injection, USP. The table below shows the volume of diluent in milliliters (mL) that must be used to achieve 200 mcg/mL concentration for infusion, and the resultant total volumes. Desired Infusion Concentration mcg/mL Milrinone 1 mg/mL (mL) Diluent (mL) Total Volume (mL) 200 10 40 50 200 20 80 100 The infusion rate should be adjusted according to hemodynamic and clinical response. Patients should be closely monitored. In controlled clinical studies, most patients showed an improvement in hemodynamic status as evidenced by increases in cardiac output and reductions in pulmonary capillary wedge pressure. Note: See “ Dosage Adjustment in Renally Impaired Patients ” Dosage may be titrated to the maximum hemodynamic effect and should not exceed 1.13 mg/kg/day. Duration of therapy should depend upon patient responsiveness. The maintenance dose in mL/hr by patient body weight (kg) may be determined by reference to the following table. Milrinone Infusion Rate (mL/hr) Using 200 mcg/mL Concentration Maintenance Dose (mcg/kg/min) Patient Body Weight (kg) 30 40 50 60 70 80 90 100 110 120 0.375 3.4 4.5 5.6 6.8 7.9 9 10.1 11.3 12.4 13.5 0.4 3.6 4.8 6 7.2 8.4 9.6 10.8 12 13.2 14.4 0.5 4.5 6 7.5 9 10.5 12 13.5 15 16.5 18 0.6 5.4 7.2 9 10.8 12.6 14.4 16.2 18 19.8 21.6 0.7 6.3 8.4 10.5 12.6 14.7 16.8 18.9 21 23.1 25.2 0.75 6.8 9 11.3 13.5 15.8 18 20.3 22.5 24.8 27 When administering milrinone lactate by continuous infusion, it is advisable to use a calibrated electronic infusion device. Intravenous drug products should be inspected visually and should not be used if particulate matter or discoloration is present. Dosage Adjustment in Renally Impaired Patients Data obtained from patients with severe renal impairment (creatinine clearance = 0 to 30 mL/min) but without congestive heart failure have demonstrated that the presence of renal impairment significantly increases the terminal elimination half-life of milrinone. Reductions in infusion rate may be necessary in patients with renal impairment. For patients with clinical evidence of renal impairment, the recommended infusion rate can be obtained from the following table: Creatinine Clearance (mL/min/1.73 m 2 ) Infusion Rate (mcg/kg/min) 5 0.2 10 0.23 20 0.28 30 0.33 40 0.38 50 0.43
Warnings
WARNINGS Whether given orally or by continuous or intermittent intravenous infusion, milrinone lactate has not been shown to be safe or effective in the longer (greater than 48 hours) treatment of patients with heart failure. In a multicenter trial of 1088 patients with Class III and IV heart failure, long-term oral treatment with milrinone lactate was associated with no improvement in symptoms and an increased risk of hospitalization and death. In this study, patients with Class IV symptoms appeared to be at particular risk of life-threatening cardiovascular reactions. There is no evidence that milrinone lactate given by long-term continuous or intermittent infusion does not carry a similar risk. The use of milrinone lactate both intravenously and orally has been associated with increased frequency of ventricular arrhythmias, including nonsustained ventricular tachycardia. Long-term oral use has been associated with an increased risk of sudden death. Hence, patients receiving milrinone lactate should be observed closely with the use of continuous electrocardiographic monitoring to allow the prompt detection and management of ventricular arrhythmias.
Contraindications
CONTRAINDICATIONS Milrinone is contraindicated in patients who are hypersensitive to it. Solutions containing dextrose may be contraindicated in patients with known allergy to corn or corn products.
Mechanism of action
CLINICAL PHARMACOLOGY: Milrinone is a positive inotrope and vasodilator, with little chronotropic activity different in structure and mode of action from either the digitalis glycosides or catecholamines. Milrinone, at relevant inotropic and vasorelaxant concentrations, is a selective inhibitor of peak III cAMP phosphodiesterase isozyme in cardiac and vascular muscle. This inhibitory action is consistent with cAMP mediated increases in intracellular ionized calcium and contractile force in cardiac muscle, as well as with cAMP dependent contractile protein phosphorylation and relaxation in vascular muscle. Additional experimental evidence also indicates that milrinone is not a beta-adrenergic agonist nor does it inhibit sodium-potassium adenosine triphosphatase activity as do the digitalis glycosides. Clinical studies in patients with congestive heart failure have shown that milrinone produces dose-related and plasma drug concentration-related increases in the maximum rate of increase of left ventricular pressure. Studies in normal subjects have shown that milrinone produces increases in the slope of the left ventricular pressure-dimension relationship, indicating a direct inotropic effect of the drug. Milrinone also produces dose-related and plasma concentration-related increases in forearm blood flow in patients with congestive heart failure, indicating a direct arterial vasodilator activity of the drug. Both the inotropic and vasodilatory effects have been observed over the therapeutic range of plasma milrinone concentrations of 100 ng/mL to 300 ng/mL. In addition to increasing myocardial contractility, milrinone improves diastolic function as evidenced by improvements in left ventricular diastolic relaxation. The acute administration of intravenous milrinone has also been evaluated in clinical trials in excess of 1,600 patients, with chronic heart failure, heart failure associated with cardiac surgery, and heart failure associated with myocardial infarction. The total number of deaths, either on therapy or shortly thereafter (24 hours) was 15, less than 0.9%, few of which were thought to be drug-related. Pharmacokinetics Following intravenous injections of 12.5 mcg/kg to 125 mcg/kg to congestive heart failure patients, milrinone had a volume of distribution of 0.38 liters/kg, a mean terminal elimination half-life of 2.3 hours, and a clearance of 0.13 liters/kg/hr. Following intravenous infusions of 0.2 mcg/kg/min to 0.70 mcg/kg/min to congestive heart failure patients, the drug had a volume of distribution of about 0.45 liters/kg, a mean terminal elimination half-life of 2.4 hours, and a clearance of 0.14 liters/kg/hr. These pharmacokinetic parameters were not dose-dependent, and the area under the plasma concentration versus time curve following injections was significantly dose-dependent. Milrinone has been shown (by equilibrium dialysis) to be approximately 70% bound to human plasma protein. The primary route of excretion of milrinone in man is via the urine. The major urinary excretions of orally administered milrinone in man are milrinone (83%) and its O-glucuronide metabolite (12%). Elimination in normal subjects via the urine is rapid, with approximately 60% recovered within the first 2 hours following dosing and approximately 90% recovered within the first 8 hours following dosing. The mean renal clearance of milrinone is approximately 0.3 liters/min, indicative of active secretion. Pharmacodynamics In patients with heart failure due to depressed myocardial function, milrinone produced a prompt dose and plasma concentration related increase in cardiac output and decreases in pulmonary capillary wedge pressure and vascular resistance, which were accompanied by mild-to-moderate increases in heart rate. Additionally, there is no increased effect on myocardial oxygen consumption. In uncontrolled studies, hemodynamic improvement during intravenous therapy with milrinone was accompanied by clinical symptomatic improvement, but the ability of milrinone to relieve symptoms has not been evaluated in controlled clinical trials. The great majority of patients experience improvements in hemodynamic function within 5 to 15 minutes of the initiation of therapy. In studies in congestive heart failure patients, milrinone when administered as a loading injection followed by a maintenance infusion produced significant mean initial increases in cardiac index of 25%, 38%, and 42% at dose regimens of 37.5 mcg/kg/0.375 mcg/kg/min, 50 mcg/kg/0.5 mcg/kg/min, and 75 mcg/kg/0.75 mcg/kg/min, respectively. Over the same range of loading injections and maintenance infusions, pulmonary capillary wedge pressure significantly decreased by 20%, 23%, and 36%, respectively, while systemic vascular resistance significantly decreased by 17%, 21%, and 37%. Mean arterial pressure fell by up to 5% at the two lower dose regimens, but by 17% at the highest dose. Patients evaluated for 48 hours maintained improvements in hemodynamic function, with no evidence of diminished response (tachyphylaxis). A smaller number of patients have received infusions of milrinone for periods up to 72 hours without evidence of tachyphylaxis. The duration of therapy should depend upon patient responsiveness. Milrinone has a favorable inotropic effect in fully digitalized patients without causing signs of glycoside toxicity. Theoretically, in cases of atrial flutter/fibrillation, it is possible that milrinone may increase ventricular response rate because of its slight enhancement of AV node conduction. In these cases, digitalis should be considered prior to the institution of therapy with milrinone. Improvement in left ventricular function in patients with ischemic heart disease has been observed. The improvement has occurred without inducing symptoms or electrocardiographic signs of myocardial ischemia. The steady-state plasma milrinone concentrations after approximately 6 to 12 hours of unchanging maintenance infusion of 0.5 mcg/kg/min are approximately 200 ng/mL. Near maximum favorable effects of milrinone on cardiac output and pulmonary capillary wedge pressure are seen at plasma milrinone concentrations in the 150 ng/mL to 250 ng/mL range. Pharmacokinetics Following intravenous injections of 12.5 mcg/kg to 125 mcg/kg to congestive heart failure patients, milrinone had a volume of distribution of 0.38 liters/kg, a mean terminal elimination half-life of 2.3 hours, and a clearance of 0.13 liters/kg/hr. Following intravenous infusions of 0.2 mcg/kg/min to 0.70 mcg/kg/min to congestive heart failure patients, the drug had a volume of distribution of about 0.45 liters/kg, a mean terminal elimination half-life of 2.4 hours, and a clearance of 0.14 liters/kg/hr. These pharmacokinetic parameters were not dose-dependent, and the area under the plasma concentration versus time curve following injections was significantly dose-dependent. Milrinone has been shown (by equilibrium dialysis) to be approximately 70% bound to human plasma protein. The primary route of excretion of milrinone in man is via the urine. The major urinary excretions of orally administered milrinone in man are milrinone (83%) and its O-glucuronide metabolite (12%). Elimination in normal subjects via the urine is rapid, with approximately 60% recovered within the first 2 hours following dosing and approximately 90% recovered within the first 8 hours following dosing. The mean renal clearance of milrinone is approximately 0.3 liters/min, indicative of active secretion. Pharmacodynamics In patients with heart failure due to depressed myocardial function, milrinone produced a prompt dose and plasma concentration related increase in cardiac output and decreases in pulmonary capillary wedge pressure and vascular resistance, which were accompanied by mild-to-moderate increases in heart rate. Additionally, there is no increased effect on myocardial oxygen consumption. In uncontrolled studies, hemodynamic improvement during intravenous therapy
Indicated ICD-10 codes
Source: RxNorm + openFDA + RxClass + FAERS · 2026
Look up another medication