Isosorbide Dinitrate and Hydralazine Hydrochloride
Managing this medication for someone you care for? Eleplan keeps diagnoses, medications and appointments in one plan.
Start free with EleplanMedication reference
Isosorbide Dinitrate and Hydralazine Hydrochloride
Nitrate Vasodilator [EPC] — ORAL
Isosorbide Dinitrate and Hydralazine Hydrochloride — Nitrate Vasodilator [EPC]. INDICATIONS AND USAGE Isosorbide dinitrate and hydralazine hydrochloride tablets is a combination of isosorbide dinitrate, a nitrate vasodilator…
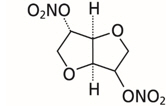
Brand names
Isosorbide dinitrate and hydralazine hydrochlorideisosorbide dinitrate and hydralazine hydrochloride
Active ingredients
HYDRALAZINE HYDROCHLORIDEISOSORBIDE DINITRATE
Indications
INDICATIONS AND USAGE Isosorbide dinitrate and hydralazine hydrochloride tablets is a combination of isosorbide dinitrate, a nitrate vasodilator, and hydralazine hydrochloride, an arteriolar vasodilator, indicated for: ● the treatment of heart failure as an adjunct therapy to standard therapy in self-identified black patients to improve survival, prolong time to hospitalization for heart failure and to improve patient-reported functional status ( 1.1 ) Limitations of use: ● There is little experience in patients with NYHA class IV heart failure ( 1.2 ) 1.1 Treatment of Heart Failure in Self-identified Black Patients Isosorbide dinitrate and hydralazine hydrochloride tablets are indicated for the treatment of heart failure as an adjunct to standard therapy in self-identified black patients to improve survival, to prolong time to hospitalization for heart failure, and to improve patient-reported functional status. 1.2 Limitations of Use There is little experience in patients with NYHA class IV heart failure.
Dosage
DOSAGE AND ADMINISTRATION Isosorbide dinitrate and hydralazine hydrochloride tablets should be initiated at a dose of one isosorbide dinitrate and hydralazine hydrochloride tablet, three times a day. Titrate to a maximum of two tablets three times daily, if tolerated. Although titration of isosorbide dinitrate and hydralazine hydrochloride tablets can be rapid (3-5 days), some patients may experience side effects and may take longer to reach their maximum tolerated dose. The dosage may be decreased to as little as one-half isosorbide dinitrate and hydralazine hydrochloride tablet three times a day if intolerable side effects occur. Efforts should be made to titrate up as soon as side effects subside. One tablet three times a day titrated to a maximum tolerated dose up to two tablets three times a day ( 2 ) Dosage may be decreased to as little as one-half tablet three times a day if intolerable side effects occur. Efforts should be made to titrate up as soon as side effects subside ( 2 )
Warnings
WARNINGS AND PRECAUTIONS May cause symptomatic hypotension ( 5.1 ) Symptomatic Lupus Erythematosus Syndromes: Consider discontinuation if clinically appropriate ( 5.2 ) Myocardial ischemia and angina ( 5.3 ) Peripheral Neuritis : May be treated with Pyridoxine ( 5.4 ) 5.1 Hypotension Symptomatic hypotension, particularly with upright posture, may occur with even small doses of isosorbide dinitrate and hydralazine hydrochloride tablets. Hypotension is most likely to occur in patients who have been volume or salt depleted; correct prior to initiation of isosorbide dinitrate and hydralazine hydrochloride tablets [see Adverse Reactions (6.1) ] . 5.2 Systemic Lupus Erythematosus Hydralazine hydrochloride has been reported to cause a drug-induced systemic lupus erythematosus (SLE) syndrome. Symptoms and signs usually regress when hydralazine hydrochloride is discontinued. 5.3 Worsening Ischemic Heart Disease Hydralazine hydrochloride can cause tachycardia and hypotension potentially leading to myocardial ischemia and angina, particularly in patients with hypertrophic cardiomyopathy. 5.4 Peripheral Neuritis Hydralazine hydrochloride has been associated with peripheral neuritis, evidenced by paresthesia, numbness, and tingling, which may be related to an antipyridoxine effect. Pyridoxine should be added to isosorbide dinitrate and hydralazine hydrochloride tablets therapy if such symptoms develop.
Contraindications
CONTRAINDICATIONS Isosorbide dinitrate and hydralazine hydrochloride tablets are contraindicated in patients who are allergic to organic nitrates. Do not use isosorbide dinitrate and hydralazine hydrochloride tablets in patients who are taking PDE-5 inhibitors, such as avanafil, sildenafil, tadalafil, or vardenafil. Concomitant use can cause severe hypotension, syncope, or myocardial ischemia [see Drug Interactions (7.1) ] . Do not use isosorbide dinitrate and hydralazine hydrochloride tablets in patients who are taking the soluble guanylate cyclase (sGC) stimulator riociguat. Concomitant use can cause hypotension. Patients who are allergic to organic nitrates ( 4 ) Use of phosphodiesterase type 5 (PDE5) inhibitors, such as avanafil, sildenafil, tadalafil, or vardenafil, or soluble guanylate cyclase (sGC) stimulator (riociguat). ( 4 )
Drug interactions
DRUG INTERACTIONS 7.1 Phosphodiesterase Inhibitors Isosorbide dinitrate and hydralazine hydrochloride tablets are contraindicated in patients who are using a selective inhibitor of cyclic guanosine monophosphate (cGMP)-specific phosphodiesterase type 5 (PDE5), PDE5 inhibitors such as avanafil, sildenafil, vardenafil, and tadalafil have been shown to potentiate the hypotensive effects of organic nitrates. Do not use isosorbide dinitrate and hydralazine hydrochloride tablets in patients who are taking the soluble guanylate cyclase (sGC) stimulator riociguat. Concomitant use can cause hypotension [see Contraindications (4) ] .
Adverse reactions
ADVERSE REACTIONS Most common adverse reactions (≥5% more on isosorbide dinitrate and hydralazine hydrochloride tablets than on placebo) were headache and dizziness ( 6.1 ) To report SUSPECTED ADVERSE REACTIONS, contact Ingenus Pharmaceuticals, LLC at 1-877-748-1970 or FDA at 1-800-FDA-1088 or www.fda.gov/medwatch. 6.1 Clinical Trials Experience Because clinical studies are conducted under widely varying conditions, adverse reaction rates observed in the clinical studies of a drug cannot be directly compared to rates in the clinical studies of another drug and may not reflect the rates observed in practice. Isosorbide dinitrate and hydralazine hydrochloride tablets have been evaluated for safety in 517 heart failure patients in A-HeFT. A total of 317 of these patients received isosorbide dinitrate and hydralazine hydrochloride tablets for at least 6 months, and 220 received isosorbide dinitrate and hydralazine hydrochloride tablets for at least 12 months. In A-HeFT, 21% of the patients discontinued isosorbide dinitrate and hydralazine hydrochloride tablets for adverse reactions compared to 12% who discontinued placebo. Overall, adverse reactions were more common in isosorbide dinitrate and hydralazine hydrochloride tablets -treated than in placebo-treated patients. Table 1 lists adverse reactions reported with an incidence, after rounding, ≥ 2% higher on isosorbide dinitrate and hydralazine hydrochloride tablets than on placebo in A-HeFT, regardless of causality. The most common reasons for discontinuing isosorbide dinitrate and hydralazine hydrochloride tablets in the A-HeFT trial was headache (7%). Table 1. Adverse Reactions Occurring in the A-HeFT Study in ≥ 2% of Patients Treated with Isosorbide Dinitrate and Hydralazine Hydrochloride Tablets Isosorbide Dinitrate and Hydralazine Hydrochloride Tablets (N=517) % Placebo (N=527) % Headache 50 21 Dizziness 32 14 Asthenia 14 11 Nausea 10 6 Hypotension 8 4 Sinusitis 4 2 Ventricular tachycardia 4 2 Paresthesia 4 2 Vomiting 4 2 Amblyopia 3 1 In the V-HeFT I and II clinical studies, a total of 587 patients with heart failure were treated with the combination of isosorbide dinitrate and hydralazine hydrochloride. The type, pattern, frequency and severity of adverse reactions reported in these studies were similar to those reported in A-HeFT, described above and no unusual adverse reactions were reported. 6.2 Postmarketing Experience The following adverse reactions have been identified during post-approval use of isosorbide dinitrate and hydralazine hydrochloride tablets . Because these reactions are reported voluntarily from a population of uncertain size, it is not always possible to reliably estimate their frequency or establish a causal relationship to drug exposure. Use of isosorbide dinitrate and hydralazine hydrochloride tablets : The following adverse reactions have been identified with use of isosorbide dinitrate and hydralazine hydrochloride tablets. Cardiac Disorders: Palpitations Ear and labyrinth disorders: Tinnitus, vertigo Eye Disorders: Eyelid edema, vision blurred Gastrointestinal Disorders: Abdominal discomfort, constipation General Disorders and Administration Site Conditions: Facial pain, flushing, chest discomfort, chest pain, peripheral edema Musculoskeletal and Connective Tissue Disorders: Pain in extremity, myalgia Nervous Disorders: Dysgeusia, hypoaesthesia, migraine, syncope Renal and Urinary Disorders: Chromaturia, pulmonary renal syndrome Respiratory, Thoracic and Mediastinal Disorders: Dyspnea Reproductive System and Breast Disorders: Erectile dysfunction Skin and Subcutaneous Tissue Disorders: Erythema, hyperhidrosis, pruritus, face swelling Use of Hydralazine Hydrochloride or Isosorbide Dinitrate: The following reactions have been reported with use of either hydralazine hydrochloride or isosorbide dinitrate. Blood and Lymphatic System Disorders: Blood dyscrasias, agranulocytosis, purpura, eosinophilia, splenomegaly. Eye Disorders: Lacrimation, conjunctivitis. Gastrointestinal Disorders: Paralytic ileus. Hepatobiliary Disorders: Hepatitis. Psychiatric Disorders: Psychotic reactions, disorientation. Renal and Urinary Disorders: Difficulty in urination.
Mechanism of action
CLINICAL PHARMACOLOGY 12.1 Mechanism of Action The mechanism of action underlying the beneficial effects of isosorbide dinitrate and hydralazine hydrochloride tablets in the treatment of heart failure has not been established. Isosorbide dinitrate is a vasodilator affecting both arteries and veins. Its dilator properties result from the release of nitric oxide and the subsequent activation of guanylyl cyclase, and ultimate relaxation of vascular smooth muscle. Several well-controlled clinical trials have used exercise testing to assess the anti-anginal efficacy of chronically-delivered nitrates. In the large majority of these trials, active agents were no more effective than placebo after 24 hours (or less) of continuous therapy. Attempts to overcome nitrate tolerance by dose escalation, even to doses far in excess of those used acutely, have consistently failed. Only after nitrates have been absent from the body for several hours is response to nitrates restored. Hydralazine hydrochloride is a selective dilator of arterial smooth muscle. Animal data suggests that hydralazine may also mitigate tolerance to nitrates. 12.2 Pharmacodynamics The basis for the beneficial clinical effects of isosorbide dinitrate and hydralazine hydrochloride tablets is not known. In a small study of patients with chronic heart failure administered single doses of hydralazine 75 mg, isosorbide dinitrate 20 mg, and the combination, the combination elicited a statistically significant decrease in pulmonary capillary wedge pressure compared to hydralazine alone. The increase in cardiac output, renal blood flow and limb blood flow with the combination, however, was not greater than with hydralazine alone. There is no study of hemodynamic effects following multiple dosing. 12.3 Pharmacokinetics Absorption Isosorbide dinitrate and hydralazine hydrochloride tablets: Following a single 75-mg oral dose of hydralazine plus 40 mg of isosorbide dinitrate to 19 healthy adults, peak plasma concentrations of hydralazine (88 ng/mL/65 kg) and isosorbide dinitrate (76 ng/mL/65 kg) were reached in 1 hour. The half-lives were about 4 hours for hydralazine and about 2 hours for isosorbide dinitrate. Peak plasma concentrations of the two active metabolites, isosorbide-2-mononitrate and isosorbide-5-mononitrate, were 98 and 364 ng/mL/65 kg, respectively, at about 2 hours. No information is currently available regarding the effect of food on the bioavailability of hydralazine or isosorbide dinitrate from isosorbide dinitrate and hydralazine hydrochloride tablets. Hydralazine hydrochloride: About 2/3 of a 50-mg dose of 14 C-hydralazine hydrochloride given in gelatin capsules was absorbed in hypertensive subjects. In patients with heart failure, mean absolute bioavailability of a single oral dose of hydralazine 75 mg varies from 10 to 26%, with the higher percentages in slow acetylators. Administration of doses escalating from 75 mg to 1000 mg three times daily to congestive heart failure patients resulted in an up to 9-fold increase in the dose normalized AUC, indicating non-linear kinetics of hydralazine, probably reflecting saturable first pass metabolism. Isosorbide dinitrate: Absorption of isosorbide dinitrate from tablets after oral dosing is nearly complete. The average bioavailability of isosorbide dinitrate is about 25%, but is highly variable (10%-90%) because of first-pass metabolism, and increases progressively during chronic therapy. Serum concentrations reach their maximum about one hour after ingestion. Distribution Hydralazine hydrochloride : After intravenous administration of hydralazine in a dose of 0.3 mg/kg, the steady-state volume of distribution in patients with congestive heart failure was 2.2 L/kg. Isosorbide dinitrate : The volume of distribution of isosorbide dinitrate is 2 to 4 L/kg. About 28% of circulating isosorbide dinitrate is protein bound. Under steady-state conditions, isosorbide dinitrate accumulates significantly in muscle (pectoral) and vein (saphenous) wall relative to simultaneous plasma concentrations. Metabolism Hydralazine is metabolized by acetylation, ring oxidation and conjugation with endogenous compounds including pyruvic acid. Acetylation occurs predominantly during the first-pass after oral administration which explains the dependence of the absolute bioavailability on the acetylator phenotype. About 50% of patients are fast acetylators and have lower exposure. After oral administration of hydralazine, the major circulating metabolites are hydralazine pyruvate hydrazone and methyltriazolophthalazine. Hydralazine is the main pharmacologically active entity; hydralazine pyruvate hydrazone has only minimal hypotensive and tachycardic activity. The pharmacological activity of methyltriazolophthalazine has not been determined. The major identified metabolite of hydralazine excreted in urine is acetylhydrazinophthalazinone. Isosorbide dinitrate undergoes extensive first-pass metabolism in the liver and is cleared at a rate of 2 to 4 L/minute with a serum half-life of about 1 hour. Isosorbide dinitrate's clearance is primarily by denitration to the 2-mononitrate (15 to 25%) and the 5-mononitrate (75 to 85%). Both metabolites have biological activity, especially the 5-mononitrate which has an overall half-life of about 5 hours. The 5-mononitrate is cleared by denitration to isosorbide, glucuronidation to the 5-mononitrate glucuronides, and by denitration/hydration to sorbitol. The 2-mononitrate appears to participate in the same metabolic pathways with a half-life of about 2 hours. Elimination Hydralazine: Metabolism is the main route for the elimination of hydralazine. Negligible amounts of unchanged hydralazine are excreted in urine. Isosorbide dinitrate: Most isosorbide dinitrate is eliminated renally as conjugated metabolites. Specific Populations No pharmacokinetic studies in special populations were conducted with isosorbide dinitrate and hydralazine hydrochloride tablets. Pharmacokinetics in special populations is based on individual components. Geriatric Patients -The pharmacokinetics of hydralazine and isosorbide dinitrate, alone or in combination, have not been determined in patients over 65 years of age. Pediatric Patients - The pharmacokinetics of hydralazine and isosorbide dinitrate, alone or in combination, have not been determined in patients below the age of 18 years. Gender - There are no studies of gender-dependent effects with hydralazine. In a single dose study with isosorbide dinitrate, no gender-dependent differences in the pharmacokinetics of isosorbide dinitrate and its mononitrate metabolites were found. Renal Impairment - The effect of renal impairment on the pharmacokinetics of hydralazine has not been determined. In a study with 49 hypertensive patients on chronic therapy with hydralazine in daily doses of 25-200 mg, the daily dose of hydralazine in 19 subjects with severely impaired renal function (creatinine clearance 5-28 mL/min) and in 17 subjects with normal renal function (creatinine clearance >100 mL/min) using a population PK approach was not different, suggesting no need for dose adjustment in patients with renal impairment. The dialyzability of hydralazine has not been determined. In three studies, renal insufficiency did not affect the pharmacokinetics of isosorbide dinitrate. Dialysis is not an effective method for removing isosorbide dinitrate or its metabolite isosorbide-5-mononitrate from the body. Hepatic Impairment - The effect of hepatic impairment on the pharmacokinetics of hydralazine alone has not been determined. Isosorbide dinitrate concentrations increase in patients with cirrhosis. Drug-Drug Interactions No pharmacokinetic drug-drug interaction studies were conducted with isosorbide dinitrate and hydralazine hydrochloride tablets. Hydralazine: Administration of hydralazine can increase the exposure to a number of drugs including beta-blockers. In healthy males administered a single oral dose of hydralaz
NDC examples
50742-24673141-012
Indicated ICD-10 codes
Treats these conditions
Source: openFDA + RxNorm · 2026
Look up another medication