Irbesartan and Hydrochlorothiazide — Angiotensin 2 Receptor Blocker [EPC]. INDICATIONS & USAGE Irbesartan and hydrochlorothiazide tablets USP are indicated for the treatment of hypertension. Irbesartan and…
Boxed warning
WARNING: FETAL TOXICITY • When pregnancy is detected, discontinue irbesartan and hydrochlorothiazide tablets as soon as possible [see Warnings and Precautions ( 5.1 ) and Use in Specific Populations ( 8.1 )]. • Drugs that act directly on the renin-angiotensin system can cause injury and death to the developing fetus [see Warnings and Precautions ( 5.1 ) and Use in Specific Populations ( 8.1 )]. WARNING: FETAL TOXICITY See full prescribing information for complete boxed warning . • When pregnancy is detected, discontinue irbesartan and hydrochlorothiazide tablets as soon as possible. ( 5.1 , 8.1 ) • Drugs that act directly on the renin-angiotensin system can cause injury and death to the developing fetus. ( 5.1 , 8.1 )
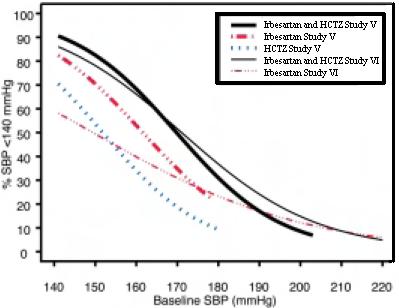
INDICATIONS & USAGE Irbesartan and hydrochlorothiazide tablets USP are indicated for the treatment of hypertension. Irbesartan and hydrochlorothiazide tablets USP may be used in patients whose blood pressure is not adequately controlled on monotherapy. Irbesartan and hydrochlorothiazide tablets USP may also be used as initial therapy in patients who are likely to need multiple drugs to achieve their blood pressure goals. The choice of irbesartan and hydrochlorothiazide tablets USP as initial therapy for hypertension should be based on an assessment of potential benefits and risks. Patients with stage 2 (moderate or severe) hypertension are at relatively high risk for cardiovascular events (such as strokes, heart attacks, and heart failure), kidney failure, and vision problems, so prompt treatment is clinically relevant. The decision to use a combination as initial therapy should be individualized and may be shaped by considerations such as the baseline blood pressure, the target goal, and the incremental likelihood of achieving goal with a combination compared with monotherapy. Data from Studies V and VI [see Clinical Studies ( 14.2 ) ] provide estimates of the probability of reaching a blood pressure goal with irbesartan and hydrochlorothiazide tablets USP compared to irbesartan or HCTZ monotherapy. The relationship between baseline blood pressure and achievement of a SeSBP <140 or <130 mmHg or SeDBP <90 or <80 mmHg in patients treated with irbesartan and hydrochlorothiazide tablets USP compared to patients treated with irbesartan or HCTZ monotherapy are shown in Figures 1a through 2b. Figure 1a: Probability of Achieving SBP <140 mmHg in Patients from Initial Therapy Studies V (Week 8) and VI (Week 7)* Figure 1b: Probability of Achieving SBP <130 mmHg in Patients from Initial Therapy Studies V (Week 8) and VI (Week 7)* Figure 2a: Probability of Achieving DBP <90 mmHg in Patients from Initial Therapy Studies V (Week 8) and VI (Week 7)* Figure 2b: Probability of Achieving DBP <80 mmHg in Patients from Initial Therapy Studies V (Week 8) and VI (Week 7)* *For all probability curves, patients without blood pressure measurements at Week 7 (Study VI) and Week 8 (Study V) were counted as not reaching goal (intent-to-treat analysis). The above graphs provide a rough approximation of the likelihood of reaching a targeted blood pressure goal (eg, Week 8 sitting systolic blood pressure ≤140 mmHg) for the treatment groups. The curve of each treatment group in each study was estimated by logistic regression modeling from all available data of that treatment group. The estimated likelihood at the right tail of each curve is less reliable due to small numbers of subjects with high baseline blood pressures. For example, a patient with a blood pressure of 180/105 mmHg has about a 25% likelihood of achieving a goal of <140 mmHg (systolic) and 50% likelihood of achieving <90 mmHg (diastolic) on irbesartan alone (and lower still likelihoods on HCTZ alone). The likelihood of achieving these goals on irbesartan and hydrochlorothiazide tablets USP rises to about 40% (systolic) or 70% (diastolic). Irbesartan and hydrochlorothiazide tablet USP is a combination of irbesartan, an angiotensin II receptor antagonist, and hydrochlorothiazide, a thiazide diuretic, indicated for hypertension: • In patients not adequately controlled with monotherapy ( 1 ) • As initial therapy in patients likely to need multiple drugs to achieve their blood pressure goals ( 1 ). figure1a.jpg figure1b.jpg figure2a.jpg figure2b.jpg
Dosage
DOSAGE AND ADMINISTRATION General Considerations Maximum effects within 2 to 4 weeks after dose change. ( 2.1 ) Renal impairment: Not recommended for patients with severe renal impairment (creatinine clearance <30 mL/min). ( 2.1 , 5.8 ) Hypertension Initiate with 150 mg/12.5 mg. Titrate to 300 mg/12.5 mg then 300 mg/25 mg if needed. ( 2.2 ) Replacement therapy: May be substituted for titrated components. ( 2.3 ) 2.1 General Considerations The side effects of irbesartan are generally rare and apparently independent of dose; those of hydrochlorothiazide are a mixture of dose-dependent (primarily hypokalemia) and dose-independent phenomena (e.g., pancreatitis), the former much more common than the latter. [See Adverse Reactions ( 6 ).] Maximum antihypertensive effects are attained within 2 to 4 weeks after a change in dose. Irbesartan and hydrochlorothiazide tablets may be administered with or without food. Irbesartan and hydrochlorothiazide tablets may be administered with other antihypertensive agents. Renal Impairment The usual regimens of therapy with irbesartan and hydrochlorothiazide tablets may be followed as long as the patient's creatinine clearance is >30 mL/min. In patients with more severe renal impairment, loop diuretics are preferred to thiazides, so irbesartan and hydrochlorothiazide tablets are not recommended. Hepatic Impairment No dosage adjustment is necessary in patients with hepatic impairment. 2.2 Add-On Therapy In patients not controlled on monotherapy with irbesartan or hydrochlorothiazide, the recommended doses of irbesartan and hydrochlorothiazide tablets, in order of increasing mean effect, are (irbesartan and hydrochlorothiazide) 150 mg/12.5 mg, 300 mg/12.5 mg, and 300 mg/25 mg. The largest incremental effect will likely be in the transition from monotherapy to 150 mg/12.5 mg. [See Clinical Studies ( 14.2 ).] 2.3 Replacement Therapy Irbesartan and hydrochlorothiazide tablets may be substituted for the titrated components. 2.4 Initial Therapy The usual starting dose is irbesartan and hydrochlorothiazide tablets 150 mg/12.5 mg once daily. The dosage can be increased after 1 to 2 weeks of therapy to a maximum of 300 mg/25 mg once daily as needed to control blood pressure [see Clinical Studies ( 14.2 )] . Irbesartan and hydrochlorothiazide tablets are not recommended as initial therapy in patients with intravascular volume depletion [see Warnings and Precautions ( 5.2 )].
Warnings
WARNINGS AND PRECAUTIONS • Hypotension: Correct volume-depletion prior to administration. (5.2) • Impaired renal function ( 5.7 ) • Thiazide diuretics may cause an exacerbation or activation of systemic lupus erythematosus. (5.4) • Secondary acute angle-closure glaucoma and/or acute myopia. ( 5.8 ) 5.1 Fetal Toxicity Pregnancy Category D Irbesartan and hydrochlorothiazide tablets can cause fetal harm when administered to a pregnant woman. Use of drugs that act on the renin-angiotensin system during the second and third trimesters of pregnancy reduces fetal renal function and increases fetal and neonatal morbidity and death. Resulting oligohydramnios can be associated with fetal lung hypoplasia and skeletal deformations. Potential neonatal adverse effects include skull hypoplasia, anuria, hypotension, renal failure, and death. When pregnancy is detected, discontinue irbesartan and hydrochlorothiazide tablets as soon as possible [see Use in Specific Populations (8.1) ]. Thiazides cross the placenta and use of thiazides during pregnancy is associated with a risk of fetal or neonatal jaundice, thrombocytopenia, and possibly other adverse reactions that have occurred in adults. 5.2 Hypotension in Volume or Salt-Depleted Patients Excessive reduction of blood pressure was rarely seen in patients with uncomplicated hypertension treated with irbesartan alone (<0.1%) or with irbesartan and hydrochlorothiazide (approximately 1%). Initiation of antihypertensive therapy may cause symptomatic hypotension in patients with intravascular volume or sodium depletion, e.g., in patients treated vigorously with diuretics or in patients on dialysis. Such volume depletion should be corrected prior to administration of antihypertensive therapy. If hypotension occurs, the patient should be placed in the supine position and, if necessary, given an intravenous infusion of normal saline. A transient hypotensive response is not a contraindication to further treatment, which usually can be continued without difficulty once the blood pressure has stabilized. 5.3 Hypersensitivity Reaction Hydrochlorothiazide Hypersensitivity reactions to hydrochlorothiazide may occur in patients with or without a history of allergy or bronchial asthma but are more likely in patients with such a history. 5.4 Systemic Lupus Erythematosus Hydrochlorothiazide Thiazide diuretics have been reported to cause exacerbation or activation of systemic lupus erythematosus. 5.5 Electrolyte and Metabolic Imbalances Irbesartan and Hydrochlorothiazide In double-blind clinical trials of various doses of irbesartan and hydrochlorothiazide, the incidence of hypertensive patients who developed hypokalemia (serum potassium <3.5 mEq/L) was 7.5% versus 6.0% for placebo; the incidence of hyperkalemia (serum potassium >5.7 mEq/L) was <1.0% versus 1.7% for placebo. No patient discontinued due to increases or decreases in serum potassium. On average, the combination of irbesartan and hydrochlorothiazide had no effect on serum potassium. Higher doses of irbesartan ameliorated the hypokalemic response to hydrochlorothiazide. Coadministration of irbesartan and hydrochlorothiazide tablets with potassium-sparing diuretics, potassium supplements, potassium-containing salt substitutes or other drugs that raise serum potassium levels may result in hyperkalemia, sometimes severe. Monitor serum potassium in such patients. Hydrochlorothiazide Hydrochlorothiazide can cause hypokalemia and hyponatremia. Hypomagnesemia can result in hypokalemia which appears difficult to treat despite potassium repletion. Drugs that inhibit the renin-angiotensin system can cause hyperkalemia. Monitor serum electrolytes periodically. Hyperuricemia may occur or frank gout may be precipitated in certain patients receiving thiazide therapy. Hydrochlorothiazide may alter glucose tolerance and raise serum levels of cholesterol and triglycerides. The antihypertensive effects of the drug may be enhanced in the post-sympathectomy patient. Thiazides may decrease urinary calcium excretion. Thiazides may cause intermittent and slight elevation of serum calcium in the absence of known disorders of calcium metabolism. Marked hypercalcemia may be evidence of hidden hyperparathyroidism. Thiazides should be discontinued before carrying out tests for parathyroid function. 5.6 Hepatic Impairment Hydrochlorothiazide Thiazides should be used with caution in patients with impaired hepatic function or progressive liver disease since minor alterations of fluid and electrolyte balance may precipitate hepatic coma. 5.7 Impaired Renal Function As a consequence of inhibiting the renin-angiotensin-aldosterone system, changes in renal function may be anticipated in susceptible individuals [see Drug Interactions (7) ]. In patients whose renal function may depend on the activity of the renin-angiotensin-aldosterone system (e.g., patients with severe congestive heart failure), treatment with ACE inhibitors has been associated with oliguria and/or progressive azotemia and (rarely) with acute renal failure and/or death. Irbesartan would be expected to behave similarly. In studies of ACE inhibitors in patients with unilateral or bilateral renal artery stenosis, increases in serum creatinine or BUN have been reported. There has been no known use of irbesartan in patients with unilateral or bilateral renal artery stenosis, but a similar effect should be anticipated. Thiazides should be used with caution in severe renal disease. In patients with renal disease, thiazides may precipitate azotemia. Cumulative effects of the drug may develop in patients with impaired renal function. 5.8 Acute Angle-Closure Glaucoma, Acute Myopia, and Choroidal Effusion Hydrochlorothiazide Hydrochlorothiazide, a sulfonamide, can cause an idiosyncratic reaction resulting in acute angle-closure glaucoma and elevated intraocular pressure with or without a noticeable acute myopic shift and/or choroidal effusions. Cases of acute angle-closure glaucoma have been reported with hydrochlorothiazide. Symptoms include acute onset of decreased visual acuity or ocular pain and typically occur within hours to weeks of drug initiation. Untreated acute angle-closure glaucoma may result in permanent vision loss. The primary treatment is to discontinue drug intake as rapidly as possible. Prompt medical or surgical treatments may need to be considered if the intraocular pressure remains uncontrolled. Risk factors for developing acute angle-closure glaucoma may include a history of sulfonamide or penicillin allergy.
Contraindications
CONTRAINDICATIONS • Irbesartan and hydrochlorothiazide tablets are contraindicated in patients who are hypersensitive to any component of this product. • Because of the hydrochlorothiazide component, this product is contraindicated in patients with anuria or hypersensitivity to other sulfonamide-derived drugs. • Do not coadminister aliskiren with irbesartan and hydrochlorothiazide tablets in patients with diabetes [see Drug Interactions ( 7 )]. • Hypersensitivity to any component of this product ( 4 ) • Anuria ( 4 ) • Hypersensitivity to sulfonamide-derived drugs ( 4 ) • Do not co-administer aliskiren with irbesartan and hydrochlorothiazide tablets in patients with diabetes ( 4 )
Drug interactions
DRUG INTERACTIONS Irbesartan Non-Steroidal Anti-Inflammatory Agents Including Selective Cyclooxygenase-2 Inhibitors (COX ‑ -2 Inhibitors) In patients who are elderly, volume-depleted (including those on diuretic therapy), or with compromised renal function, coadministration of NSAIDS, including selective COX-2 inhibitors with angiotensin II receptor antagonists, including irbesartan, may result in deterioration of renal function, including possible acute renal failure. These effects are usually reversible. Monitor renal function periodically in patients receiving irbesartan and NSAID therapy. The antihypertensive effect of angiotensin II receptor antagonist, including irbesartan may be attenuated by NSAIDS including selective COX-2 inhibitors. Dual Blockade of the Renin-Angiotensin System (RAS) Dual blockade of the RAS with angiotensin-receptor blockers, ACE inhibitors, or aliskiren is associated with increased risks of hypotension, hyperkalemia, and changes in renal function (including acute renal failure) compared to monotherapy. Closely monitor blood pressure, renal function, and electrolytes in patients on irbesartan and hydrochlorothiazide tablets and other agents that affect the RAS. In most patients no benefit has been associated with using two RAS inhibitors concomitantly. In general, avoid combined use of RAS inhibitors. Do not coadminister aliskiren with irbesartan and hydrochlorothiazide tablets in patients with diabetes. Avoid use of aliskiren with irbesartan and hydrochlorothiazide tablets in patients with renal impairment (GFR <60 mL/min). Hydrochlorothiazide When administered concurrently the following drugs may interact with thiazide diuretics: Alcohol, Barbiturates, or Narcotics : potentiation of orthostatic hypotension may occur. Antidiabetic Drugs (oral agents and insulin) : dosage adjustment of the antidiabetic drug may be required. Other Antihypertensive Drugs : additive effect or potentiation. Cholestyramine and Colestipol Resins : absorption of hydrochlorothiazide is impaired in the presence of anionic exchange resins. Single doses of either cholestyramine or colestipol resins bind the hydrochlorothiazide and reduce its absorption from the gastrointestinal tract by up to 85% and 43%, respectively. Irbesartan and hydrochlorothiazide tablets should be taken at least one hour before or four hours after these medications. Corticosteroids, ACTH : intensified electrolyte depletion, particularly hypokalemia. Pressor Amines (eg, Norepinephrine) : possible decreased response to pressor amines but not sufficient to preclude their use. Skeletal Muscle Relaxants, Nondepolarizing (eg, Tubocurarine) : possible increased responsiveness to the muscle relaxant. Lithium: Increases in serum lithium concentrations and lithium toxicity have been reported with concomitant use of irbesartan or thiazide diuretics. Monitor lithium levels in patients receiving irbesartan and hydrochlorothiazide tablets and lithium. Non-steroidal Anti-inflammatory Drugs : in some patients, the administration of a non-steroidal anti-inflammatory agent can reduce the diuretic, natriuretic, and antihypertensive effects of loop, potassium-sparing and thiazide diuretics. Therefore, when irbesartan and hydrochlorothiazide tablets and non-steroidal anti-inflammatory agents are used concomitantly, the patient should be observed closely to determine if the desired effect of the diuretic is obtained. Carbamazepine : concomitant use of carbamazepine and hydrochlorothiazide has been associated with the risk of symptomatic hyponatremia. Electrolytes should be monitored during concomitant use. • NSAIDS and selective COX-2 inhibitors: May lead to increased risks of renal impairment and loss of antihypertensive effect. Monitor renal function periodically. • Dual blockade of the renin-angiotensin system: Increased risk of renal impairment, hypotension, and hyperkalemia. • Antidiabetic Drugs: Dosage adjustment of antidiabetic may be required • Cholestyramine and colestipol: Reduced absorption of thiazides •Lithium: Increases in serum lithium concentrations and lithium toxicity • NSAIDs: Can reduce diuretic, natriuretic, and antihypertensive effects of diuretics and increase risk of renal impairment. • Carbamazepine: Increased risk of hyponatremia.
Adverse reactions
ADVERSE REACTIONS Most common adverse events (≥5% on AVALIDE and more often than on placebo) are dizziness, fatigue, and musculoskeletal pain. ( 6.1 ) To report SUSPECTED ADVERSE REACTIONS, contact sanofi-aventis U.S. LLC at 1-800-633-1610 or FDA at 1-800-FDA-1088 or www.fda.gov/medwatch. 6.1 Clinical Trials Experience Because clinical trials are conducted under widely varying conditions, adverse reaction rates observed in the clinical trials of a drug cannot be directly compared to rates in the clinical trials of another drug and may not reflect the rates observed in practice. The adverse reaction information from clinical trials does, however, provide a basis for identifying the adverse events that appear to be related to drug use and for approximating rates. Irbesartan and Hydrochlorothiazide AVALIDE tablets have been evaluated for safety in 1694 patients treated for essential hypertension in 6 clinical trials. In Studies I through IV with AVALIDE, no adverse events peculiar to this combination drug product have been observed. Adverse events have been limited to those that were reported previously with irbesartan or hydrochlorothiazide (HCTZ). The overall incidence of adverse events was similar with the combination and placebo. In general, treatment with AVALIDE was well tolerated. For the most part, adverse events have been mild and transient in nature and have not required discontinuation of therapy. In controlled clinical trials, discontinuation of AVALIDE therapy due to clinical adverse events was required in only 3.6%. This incidence was significantly less (p=0.023) than the 6.8% of patients treated with placebo who discontinued therapy. In these double-blind controlled clinical trials, the following adverse events reported with AVALIDE occurred in ≥1% of patients, and more often on the irbesartan and hydrochlorothiazide combination than on placebo, regardless of drug relationship: Irbesartan/HCTZ (n=898) (%) Placebo (n=236) (%) Irbesartan (n=400) (%) HCTZ (n=380) (%) Body as a Whole Chest Pain 2 1 2 2 Fatigue 6 3 4 3 Influenza 3 1 2 2 Cardiovascular Edema 3 3 2 2 Tachycardia 1 0 1 1 Gastrointestinal Abdominal Pain 2 1 2 2 Dyspepsia/heartburn 2 1 0 2 Nausea/vomiting 3 0 2 2 Immunology Allergy 1 0 1 1 Musculoskeletal Musculoskeletal Pain 6 5 6 10 Nervous System Dizziness 8 4 6 5 Dizziness Orthostatic 1 0 1 1 Renal/Genitourinary Abnormality Urination 2 1 1 2 The following adverse events were also reported at a rate of 1% or greater, but were as, or more, common in the placebo group: headache, sinus abnormality, cough, URI, pharyngitis, diarrhea, rhinitis, urinary tract infection, rash, anxiety/nervousness, and muscle cramp. Adverse events occurred at about the same rates in men and women, older and younger patients, and black and non-black patients. Adverse events in Studies V and VI were similar to those described above in Studies I through IV. Irbesartan Other adverse events that have been reported with irbesartan, without regard to causality, are listed below: Body as a Whole: fever, chills, orthostatic effects, facial edema, upper extremity edema Cardiovascular: flushing, hypertension, cardiac murmur, myocardial infarction, angina pectoris, hypotension, syncope, arrhythmic/conduction disorder, cardiorespiratory arrest, heart failure, hypertensive crisis Dermatologic: pruritus, dermatitis, ecchymosis, erythema face, urticaria Endocrine/Metabolic/Electrolyte Imbalances: sexual dysfunction, libido change, gout Gastrointestinal: diarrhea, constipation, gastroenteritis, flatulence, abdominal distention Musculoskeletal/Connective Tissue: musculoskeletal trauma, extremity swelling, muscle cramp, arthritis, muscle ache, musculoskeletal chest pain, joint stiffness, bursitis, muscle weakness Nervous System: anxiety/nervousness, sleep disturbance, numbness, somnolence, vertigo, emotional disturbance, depression, paresthesia, tremor, transient ischemic attack, cerebrovascular accident Renal/Genitourinary: prostate disorder Respiratory: cough, upper respiratory infection, epistaxis, tracheobronchitis, congestion, pulmonary congestion, dyspnea, wheezing Special Senses: vision disturbance, hearing abnormality, ear infection, ear pain, conjunctivitis Hydrochlorothiazide Other adverse events that have been reported with hydrochlorothiazide, without regard to causality, are listed below: Body as a Whole: weakness Digestive: pancreatitis, jaundice (intrahepatic cholestatic jaundice), sialadenitis, cramping, gastric irritation Hematologic: aplastic anemia, agranulocytosis, leukopenia, hemolytic anemia, thrombocytopenia Hypersensitivity: purpura, photosensitivity, urticaria, necrotizing angiitis (vasculitis and cutaneous vasculitis), fever, respiratory distress including pneumonitis and pulmonary edema, anaphylactic reactions Metabolic: hyperglycemia, glycosuria, hyperuricemia Musculoskeletal: muscle spasm Nervous System/Psychiatric: restlessness Renal: renal failure, renal dysfunction, interstitial nephritis Skin: erythema multiforme including Stevens-Johnson syndrome, exfoliative dermatitis including toxic epidermal necrolysis Special Senses: transient blurred vision, xanthopsia Initial Therapy In the moderate hypertension Study V (mean SeDBP between 90 and 110 mmHg), the types and incidences of adverse events reported for patients treated with AVALIDE were similar to the adverse event profile in patients on initial irbesartan or HCTZ monotherapy. There were no reported events of syncope in the AVALIDE treatment group and there was one reported event in the HCTZ treatment group. The incidences of prespecified adverse events on AVALIDE, irbesartan, and HCTZ, respectively, were: 0.9%, 0%, and 0% for hypotension; 3.0%, 3.8%, and 1.0% for dizziness; 5.5%, 3.8%, and 4.8% for headache; 1.2%, 0%, and 1.0% for hyperkalemia; and 0.9%, 0%, and 0% for hypokalemia. The rates of discontinuation due to adverse events on AVALIDE, irbesartan alone, and HCTZ alone were 6.7%, 3.8%, and 4.8%. In the severe hypertension (SeDBP ≥110 mmHg) Study VI, the overall pattern of adverse events reported through 7 weeks of follow-up was similar in patients treated with AVALIDE as initial therapy and in patients treated with irbesartan as initial therapy. The incidences of the prespecified adverse events on AVALIDE and irbesartan, respectively, were: 0% and 0% for syncope; 0.6% and 0% for hypotension; 3.6% and 4.0% for dizziness; 4.3% and 6.6% for headache; 0.2% and 0% for hyperkalemia; and 0.6% and 0.4% for hypokalemia. The rates of discontinuation due to adverse events were 2.1% and 2.2%. [See Clinical Studies (14.2) .] 6.2 Postmarketing Experience The following adverse reactions have been identified during postapproval use of AVALIDE. Because these reactions are reported voluntarily from a population of uncertain size, it is not always possible to reliably estimate their frequency or establish a causal relationship to drug exposure. Decisions to include these reactions in labeling are typically based on one or more of the following factors: (1) seriousness of the reaction, (2) frequency of reporting, or (3) strength of causal connection to AVALIDE. Irbesartan and hydrochlorothiazide Blood and lymphatic system: Thrombocytopenia Hepatobiliary: Hepatitis, Jaundice Renal and urinary: Impaired renal function including renal failure Skin and subcutaneous tissue: Urticaria Irbesartan Blood and lymphatic system: Anemia Ear and labyrinth: Tinnitus Gastrointestinal: Intestinal angioedema Skin and subcutaneous tissue: Angioedema (involving swelling of the face, lips, pharynx, and/or tongue) Immune system: Anaphylactic reaction including anaphylactic shock Investigations: Increased CPK (Creatine Phosphokinase) Metabolism and nutrition: Hyperkalemia, Hypoglycemia in diabetic patients Hydrochlorothiazide Eye: Acute angle-closure glaucoma, Acute myopia, and Choroidal effusion Non-melanoma Skin Cancer Hydrochlorothiazide is associated with an increased risk of non-melanoma skin cancer. In a study cond
Mechanism of action
CLINICAL PHARMACOLOGY 12.1 Mechanism of Action Irbesartan Angiotensin II is a potent vasoconstrictor formed from angiotensin I in a reaction catalyzed by angiotensin-converting enzyme (ACE, kininase II). Angiotensin II is the principal pressor agent of the RAS and also stimulates aldosterone synthesis and secretion by adrenal cortex, cardiac contraction, renal resorption of sodium, activity of the sympathetic nervous system, and smooth muscle cell growth. Irbesartan blocks the vasoconstrictor and aldosterone-secreting effects of angiotensin II by selectively binding to the AT 1 angiotensin II receptor. There is also an AT 2 receptor in many tissues, but it is not involved in cardiovascular homeostasis. Irbesartan is a specific competitive antagonist of AT 1 receptors with a much greater affinity (more than 8500-fold) for the AT 1 receptor than for the AT 2 receptor, and no agonist activity. Blockade of the AT 1 receptor removes the negative feedback of angiotensin II on renin secretion, but the resulting increased plasma renin activity and circulating angiotensin II do not overcome the effects of irbesartan on blood pressure. Irbesartan does not inhibit ACE or renin or affect other hormone receptors or ion channels known to be involved in the cardiovascular regulation of blood pressure and sodium homeostasis. Because irbesartan does not inhibit ACE, it does not affect the response to bradykinin; whether this has clinical relevance is not known. Hydrochlorothiazide Hydrochlorothiazide is a thiazide diuretic. Thiazides affect the renal tubular mechanisms of electrolyte reabsorption, directly increasing excretion of sodium and chloride in approximately equivalent amounts. Indirectly, the diuretic action of hydrochlorothiazide reduces plasma volume, with consequent increases in plasma renin activity, increases in aldosterone secretion, increases in urinary potassium loss, and decreases in serum potassium. The renin-aldosterone link is mediated by angiotensin II, so coadministration of an angiotensin II receptor antagonist tends to reverse the potassium loss associated with these diuretics. The mechanism of the antihypertensive effect of thiazides is not fully understood. 12.2 Pharmacodynamics Irbesartan In healthy subjects, single oral irbesartan doses of up to 300 mg produced dose-dependent inhibition of the pressor effect of angiotensin II infusions. Inhibition was complete (100%) 4 hours following oral doses of 150 mg or 300 mg and partial inhibition was sustained for 24 hours (60% and 40% at 300 mg and 150 mg, respectively). In hypertensive patients, angiotensin II receptor inhibition following chronic administration of irbesartan causes a 1.5-fold to 2-fold rise in angiotensin II plasma concentration and a 2-fold to 3-fold increase in plasma renin levels. Aldosterone plasma concentrations generally decline following irbesartan administration, but serum potassium levels are not significantly affected at recommended doses. In hypertensive patients, chronic oral doses of irbesartan (up to 300 mg) had no effect on glomerular filtration rate, renal plasma flow or filtration fraction. In multiple dose studies in hypertensive patients, there were no clinically important effects on fasting triglycerides, total cholesterol, HDL-cholesterol, or fasting glucose concentrations. There was no effect on serum uric acid during chronic oral administration and no uricosuric effect. Hydrochlorothiazide After oral administration of hydrochlorothiazide, diuresis begins within 2 hours, peaks in about 4 hours and lasts about 6 to 12 hours. Drug Interactions Hydrochlorothiazide Alcohol, barbiturates, or narcotics: Potentiation of orthostatic hypotension may occur. Skeletal muscle relaxants: Possible increased responsiveness to muscle relaxants such as curare derivatives. Corticosteroids, ACTH: Intensified electrolyte depletion, particularly hypokalemia. Pressor amines (e.g., norepinephrine): Possible decreased response to pressor amines but not sufficient to preclude their use. 12.3 Pharmacokinetics Irbesartan Irbesartan is an orally active agent that does not require biotransformation into an active form. The oral absorption of irbesartan is rapid and complete with an average absolute bioavailability of 60% to 80%. Following oral administration of irbesartan, peak plasma concentrations of irbesartan are attained at 1.5 to 2 hours after dosing. Food does not affect the bioavailability of irbesartan. Irbesartan exhibits linear pharmacokinetics over the therapeutic dose range. The terminal elimination half-life of irbesartan averaged 11 to 15 hours. Steady-state concentrations are achieved within 3 days. Limited accumulation of irbesartan (<20%) is observed in plasma upon repeated once-daily dosing. Hydrochlorothiazide When plasma levels have been followed for at least 24 hours, the plasma half-life has been observed to vary between 5.6 and 14.8 hours. Metabolism and Elimination Irbesartan Irbesartan is metabolized via glucuronide conjugation and oxidation. Following oral or intravenous administration of 14 C-labeled irbesartan, more than 80% of the circulating plasma radioactivity is attributable to unchanged irbesartan. The primary circulating metabolite is the inactive irbesartan glucuronide conjugate (approximately 6%). The remaining oxidative metabolites do not add appreciably to irbesartan’s pharmacologic activity. Irbesartan and its metabolites are excreted by both biliary and renal routes. Following either oral or intravenous administration of 14 C-labeled irbesartan, about 20% of radioactivity is recovered in the urine and the remainder in the feces, as irbesartan or irbesartan glucuronide. In vitro studies of irbesartan oxidation by cytochrome P450 isoenzymes indicated irbesartan was oxidized primarily by 2C9; metabolism by 3A4 was negligible. Irbesartan was neither metabolized by, nor did it substantially induce or inhibit, isoenzymes commonly associated with drug metabolism (1A1, 1A2, 2A6, 2B6, 2D6, 2E1). There was no induction or inhibition of 3A4. Hydrochlorothiazide Hydrochlorothiazide is not metabolized but is eliminated rapidly by the kidney. At least 61% of the oral dose is eliminated unchanged within 24 hours. Distribution Irbesartan Irbesartan is 90% bound to serum proteins (primarily albumin and α 1 -acid glycoprotein) with negligible binding to cellular components of blood. The average volume of distribution is 53 to 93 liters. Total plasma and renal clearances are in the range of 157 to 176 mL/min and 3.0 to 3.5 mL/min, respectively. With repetitive dosing, irbesartan accumulates to no clinically relevant extent. Studies in animals indicate that radiolabeled irbesartan weakly crosses the blood-brain barrier and placenta. Irbesartan is excreted in the milk of lactating rats. Hydrochlorothiazide Hydrochlorothiazide crosses the placental but not the blood-brain barrier and is excreted in breast milk. Specific Populations Pediatric Irbesartan and hydrochlorothiazide pharmacokinetics have not been investigated in patients <18 years of age. Gender No gender-related differences in pharmacokinetics were observed in healthy elderly (age 65 to 80 years) or in healthy young (age 18 to 40 years) subjects. In studies of hypertensive patients, there was no gender difference in half-life or accumulation, but somewhat higher plasma concentrations of irbesartan were observed in females (11% to 44%). No gender-related dosage adjustment is necessary. Geriatric In elderly subjects (age 65 to 80 years), irbesartan elimination half-life was not significantly altered, but AUC and C max values were about 20% to 50% greater than those of young subjects (age 18 to 40 years). No dosage adjustment is necessary in the elderly. Race In healthy black subjects, irbesartan AUC values were approximately 25% greater than whites; there were no differences in C max values. Renal insufficiency The pharmacokinetics of irbesartan were not altered in patients with renal impairment or in pat